
Español Respiratory syncytial virus (RSV) is a common infection that targets the lungs and respiratory system. It’s so common that many children have been infected with the virus before their second birthday. But RSV doesn’t just make children sick, the virus can also infect adults. RSV disrupts cell linings in the respiratory tract and when the immune system launches an attack, it stirs up inflammation and an overproduction of mucus. Airways become narrow and clogged with mucus, cell debris and fluid, which can make breathing feel like blowing through a plastic straw or wheezing like a deflated accordion. While many infections are mild, infants under 2 months, all adults over age 75 and adults over 50 with chronic conditions are at higher risk for serious infections and hospitalizations. How does RSV spread? RSV is contagious and spreads like the flu. Coughing and sneezing blast tiny microdroplets into the air and onto surfaces. You can get the virus when you breathe in these microdroplets or they get into your eyes, nose or mouth because someone coughs and sneezes near you, or you touch a contaminated surface and then touch your face before washing your hands. Read: Is It Covid, RSV or the Flu? >> Who should get the RSV vaccine? In the U.S., the Centers for Disease Control and Prevention (CDC) recommends an RSV vaccine for any adult 75 and older, or those over 50 with conditions that put them at higher risk for severe RSV disease that can lead to hospitalizations. What conditions increase the risk of severe illness from RSV? The RSV virus can be ruthless in people with impaired organ function or compromised immune systems. Several conditions put you at high risk for getting severely ill from the virus. These conditions include: Check with your healthcare provider (HCP) if you’re uncertain about your risk status. How often do you need a RSV vaccine? Currently, the CDC recommends just one RSV vaccine as an adult over age 75 or an adult ages 50-74 who is at increased risk of severe illness from RSV. You should receive this vaccine even if you received it while pregnant. When is the best time to get an RSV vaccine? RSV season is generally October through March, although that can vary depending on what part of the country you live in. The best time to get vaccinated is late summer or early fall before RSV season starts, but you can get vaccinated at any time. Ask your HCP when they recommend getting the shot in your area. What are the RSV vaccine side effects? RSV vaccines have similar side effects as other vaccines, which are usually mild, and can include: Pain at the injection site Fatigue Fever Headache Nausea Joint or muscle pain What are the benefits of the RSV vaccine? The benefits of getting vaccinated far outweigh the risks. Getting the RSV vaccine is the best way to prevent serious illness and complications from serious illness, like a cardiac event triggered by inflammation from the virus. It also substantially reduces hospitalization rates for RSV in older adults. And one study even indicated that getting the RSV vaccine can lower the risk of dementia later in life. The benefits of getting the RSV vaccine are similar for pregnant people — preventing serious illness and hospitalization. It also provides protection to the fetus when the vaccine is given sometime between 32 to 36 weeks of pregnancy. Maternal vaccination has shown a 68% reduction in infant hospitalization in newborns who get RSV. If a woman didn’t receive the vaccine while pregnant, her infant can get a long-acting infant RSV antibody injection after they’re born to protect them from developing severe disease and keep them out of the hospital. In addition to health benefits, getting vaccinated can help your community. When populations are well vaccinated, adults miss less work, students miss less school, and hospitals are less stressed by disease outbreaks. This educational resource was created with support from Moderna. From Your Site Articles Related Articles Around the Web Source link
Study: Moxifloxacin bests azithromycin in treating M . gen italium
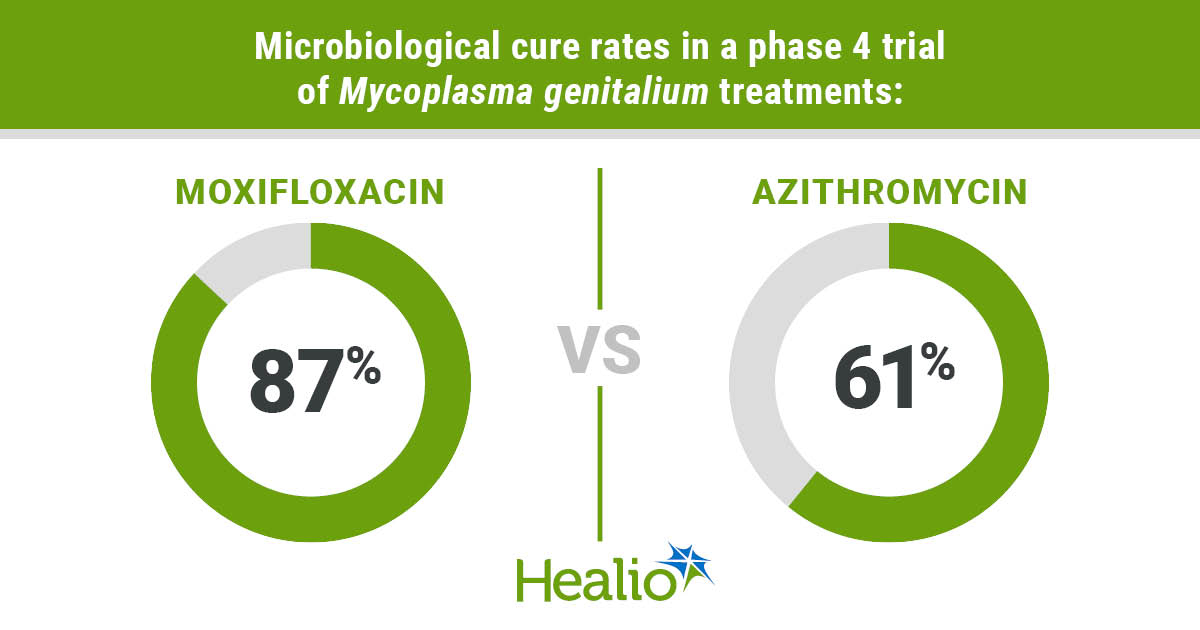
Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Key takeaways: A phase 4 trial demonstrated an 87% cure rate for moxifloxacin in treating Mycoplasma genitalium. A researcher said it is “not surprising” moxifloxacin performed better than azithromycin. A study that compared the efficacy of moxifloxacin vs. azithromycin in treating Mycoplasma genitalium — an STI with a rising resistance to antibiotics — showed that moxifloxacin was the clear winner. In the phase 4 randomized trial, a 10-day regimen of moxifloxacin yielded a significantly higher microbiologic cure rate compared with a 6-day regimen of azithromycin (87% vs. 61.2%; absolute risk difference, 25.8%; 95% CI, 16.5%-35.2%), supporting moxifloxacin as an empiric first-line treatment. Data derived from Rossotti R, et al. Clin Infect Dis. 2026;doi:10.1093/cid/ciag317. The study pointed out, however, that azithromycin “showed comparable efficacy” among heterosexual participants. “It is not surprising that moxifloxacin performs better than azithromycin in a population largely composed of” gay, bisexual and other men who have sex with men (MSM), the study’s lead author, Roberto Rossotti, MD, associate professor of infectious diseases at University of Verona in Italy, told Healio. “But it is surprising that this performance is comparable to that observed with the resistance-guided approach, saving 4 days of treatment and one class of antibiotics.” M. genitalium is a common STI that causes a burning while urinating and discharge from the vagina or penis, according to the CDC.eatment has become tricky due to a macrolide resistance to azithromycin, once a first-line treatment, with resistance rising from 10% before 2010 to 51% in 2016-2017, researchers reported. Rossotti and colleagues conducted the trial in a tertiary care hospital located in Milan from January 2018 to June 2024. They randomly assigned 358 patients (median age, 36 years; 96.6% men; 94.1% gay, bisexual and other MSM; 5.9% heterosexual) to moxifloxacin (53.9%; n = 193) or azithromycin (46.1%; n = 165). Moxifloxacin was administered as a once-daily 400 mg dose for 10 days, whereas azithromycin was given as a 500 mg daily dose for 6 days. In addition to the main finding, the study showed a success rate of moxifloxacin in retreatment. Specifically, 96.8% of participants (30 out of 31) who failed an initial round of azithromycin were cured with moxifloxacin, whereas a second round of azithromycin only cured 60% of individuals (nine out of 15; P = .003). The study also found that co-administering doxycycline did not enhance treatment outcomes in either group. “A 10-day course of moxifloxacin may achieve 90% microbiologic success even if a resistance test is not available,” Rossotti said. M. genitalium is a leading cause of non-gonococcal urethritis in men and linked to cervicitis in women, the CDC reported. Meanwhile, Rossotti said the study gives clinicians hope in treating the stubborn infection. “We may be reassured about the everyday clinical management of (M. genitalium) based on a relatively short course of quinolone therapy alone,” he said. For more information: Roberto Rossotti, MD, can be reached at infectiousdisease@healio.com. Perspective Back to Top Management of M. genitalium remains challenging for many reasons, including limited access to macrolide resistance testing despite a high prevalence of resistant infections. The results of this study comparing monotherapy for M. genitalium with azithromycin vs. moxifloxacin illustrate the consequences of this prevalence; rates of azithromycin treatment failure roughly correspond to reported rates of macrolide resistance in Europe. U.S. and U.K. guidelines only recommend azithromycin use when M. genitalium susceptibility is confirmed, and after a preceding week of doxycycline. This strategy enables successful use of azithromycin in M. genitalium treatment while avoiding de novo resistance, and stewards moxifloxacin, currently the only other widely available therapy for this infection in the U.S. Where resistance testing is not available, sequential therapy with doxycycline and moxifloxacin remains the standard for patients who are not pregnant. The utility of doxycycline (and other agents) as a part of moxifloxacin-based M. genitalium regimens merits further study, especially as rates of quinolone resistance rise. The relatively small number of patients receiving doxycycline in this study limits conclusions as to its role (or lack thereof) alongside moxifloxacin. Future efforts to improve M. genitalium therapy need to address access to macrolide (and potentially fluoroquinolone) resistance testing and rigorously compare treatment strategies that minimize antibiotic exposure and steward available agents without sacrificing efficacy. Jacob McLean, DO Adult Infectious Disease Physician and Assistant Professor of Medicine at New York Presbyterian Columbia University Irving Medical Center. Disclosures: McLean reports no relevant financial disclosures. Published by: Ask a clinical question and tap into Healio AI’s knowledge base. PubMed, enrolling/recruiting trials, guidelines Clinical Guidance, Healio CME, FDA news Healio’s exclusive daily news coverage of clinical data Learn more Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Source link

What is hot yoga? – HealthyWomen
Like most working moms, Gillian Russell doesn’t get a lot of time to herself. She has every good excuse to not show up to a 6:30 a.m. workout. And yet numerous days a week she shows up early to a hot yoga class. “I love room-temperature yoga too, but hot yoga makes my body feel so open and relaxed,” Russell said. “Like melted butter. It’s hard work and you have to push through some discomfort, but the reward is delightful.” Feeling like melted butter sounds pretty wonderful to me, but I’m going to need a lot more information on what exactly hot yoga is before I sign up for a class because honestly, pushing through physical discomfort in a hot room sounds not terribly inviting. I spoke with certified hot yoga instructors to get a thorough understanding of how the practice works, how it can be beneficial and what you should know before booking a class. Hot yoga has a dark past, but is now grounded in wellness Hot yoga came to be a thing in the western world when Bikram Choudhury, a controversial yoga practitioner, imported a version of the practice from India and stamped the name “Bikram” on it in the early 1970s. Long story short: Choudhury, who has been the subject of civil suits alleging sexual assault and discrimination against racial and sexual minorities, was basically just trying to build a cult and a monopoly – but Bikram Yoga is still the most popular form of hot yoga in the U.S., and it’s no longer associated with the controversial man. Bikram Yoga is a hatha-based practice, meaning it’s done slowly, with a focus on balance and alignment. Every class follows the same sequence of 26 postures and two breathing exercises in a room heated to 105° with around 40% humidity. In its original incarnation, Bikram Yoga was intended to be a pretty miserable experience, with Choudhury famously calling his heated spaces “torture chambers.” Drinking water as needed or taking a break on your terms was forbidden. “It was not handled as it should have been,” said Kelly Isaac, certified hot yoga instructor and co-founder of ID Hot Yoga, New York City. “But in 2026 these types of hot yoga classes are few and far between. The priority is now on wellness and on taking care of yourself.” The health benefits of hot yoga are there — but not necessarily unique to the practice There’s growing research suggesting that hot yoga has a number of health benefits. One study published by Sports Medicine in 2025 found that consistent hot yoga practice may improve aspects of heart and metabolic health, along with supporting bone density — all areas where women need as much help as they can get as they age. Then there’s the mounting research that speaks to the role hot yoga can play in fostering psychological wellness and stress reduction. The only issue is that there’s not much evidence to say that hot yoga does any of this better than non-heated yoga. So you could say, “Well I don’t need to bother with a hot room to get the full benefits of yoga” and nobody could rightly say you’re wrong. But they may say you’re missing the point. A big draw of hot yoga for the people who love it is the heat itself. “I tend to run cold, and there’s something very cathartic about just being in the heat,” said Laura Lusson, an E-RYT 500 and RPYT-certified yoga instructor and co-owner of The Space Between in Chicago. “I feel I can move more freely. My range of motion is greater, and I stay aware to avoid overreaching. Sweating feels good.” Hot yoga is already intense, but some studios are making it even more so Nowadays you’ll find studios and gyms offering all types of hot yoga, including vinyasa, which is more fast-paced and flow-based than hatha. You’ll even see hot pilates classes and hot HIIT classes at some gyms and studios. But aspiring hot yogi beware: There’s valid controversy around making an already challenging workout more intense with added heat. “Vinyasa is fast and hard without the heat, and the breath you use builds an internal fire,” Isaac said. “So vinyasa should not be carried out in a hot room, but it is in many studios across the world.” But some hot yogi devotees wouldn’t have their yoga workouts any other way. Russell is among them. That early morning class she never misses? It’s a hot vinyasa flow. Now, since Russell enjoys the class and is in great physical shape, there’s no reason she should quit, but until you’re acclimated to hot yoga, stick with a more traditional hatha-based class. What to know before booking a hot yoga class Curious about trying hot yoga? The next step on your journey is getting medical clearance from your healthcare provider (HCP). It may be a pain to get, but this is really the only safe way to get started with hot yoga. Note that hot yoga is not considered safe for pregnant women at any stage in their pregnancy, and your HCP may recommend a different type of exercise if you have a heart condition or are prone to high blood pressure, because hot yoga (even the slow kind) increases your heart rate. Dehydration is the most common risk associated with hot yoga, so take all measures to prevent it. “Based on my personal experience, the key is to go in hydrated but not overly full of water (which can make you feel sick) and to hydrate afterward,” Lusson said. “I like coconut water for electrolytes.” Bear in mind that hot yoga is supposed to be challenging, but not agonizing. It’s good to feel a stretch deeply but not to the point of being in pain. “My motto in teaching: If something doesn’t feel good, or if you feel ill, stop what you’re doing,” Lusson said. “The teacher will talk with you and will help.” Finally, know
Olezarsen reduces triglycerides, acute pancreatitis events
Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Key takeaways: In patients with severe hypertriglyceridemia, olezarsen reduced triglycerides compared with placebo at 12 months. Olezarsen also lowered risk for acute pancreatitis events compared with placebo. In patients with severe hypertriglyceridemia, olezarsen lowered triglycerides and reduced acute pancreatitis events compared with placebo, researchers reported at the European Atherosclerosis Society Congress. André Zimerman, MD, PhD, professor of cardiology and head of clinical trials at Hospital Moinhos de Vento, Moinhos de Vento Medical School, Porto Alegre, Rio Grande do Sul, Brazil, presented on behalf of the TIMI Study Group a pooled analysis of 455 patients (mean age, 52 years; 20% women) with severe hypertriglyceridemia, defined as triglyceride level more than 880 mg/dL, or 10 mmol/L, from the CORE-TIMI 72a and CORE2-TIMI 72b trials. Patients were randomly assigned to olezarsen (Tryngolza, Ionis) 50 mg, olezarsen 80 mg or placebo. André Zimerman “Patients with severe hypertriglyceridemia are at high risk for acute pancreatitis, but randomized evidence showing that pharmacologic triglyceride lowering reduces pancreatitis events has been limited,” Zimerman told Healio. “Currently available therapies, such as fibrates and omega-3 fatty acids, have a modest triglyceride-lowering effect and have not been shown to prevent acute pancreatitis.” As Healio previously reported, olezarsen was approved by the FDA in 2024 for treatment of patients with familial chylomicronemia syndrome, but has not yet been approved for treatment of severe hypertriglyceridemia in the U.S. At 6 months, compared with placebo, olezarsen 50 mg lowered triglycerides by 58.8% and olezarsen 80 mg lowered triglycerides by 65.5% (P < .001 for both), Zimerman said during a presentation. At 6 months, 85% of the olezarsen 50 mg group and 86% of the olezarsen 80 mg group reached a triglyceride level less than 880 mg/dL compared with 43% of the placebo group, and both olezarsen groups reached triglyceride levels less than 500 mg/dL and less than 150 mg/dL at greater rates than the placebo group (P < .001 for all comparisons), according to the researchers. Both olezarsen groups also had lower levels of apolipoprotein C-III, remnant cholesterol and non-HDL at 6 months compared with the placebo group (P < .001 for all comparisons), Zimerman and colleagues found. Acute pancreatitis events over 12 months were lower in the pooled olezarsen group than in the placebo group (RR = 0.15; 95% CI, 0.06-0.43; P < .001; number needed to treat to prevent one event at 12 months = 9), Zimerman said. “Targeting ApoC-III with olezarsen meaningfully lowers triglycerides and markedly reduces pancreatitis risk in patients with severe hypertriglyceridemia, a population with substantial residual risk despite available therapies,” Zimerman told Healio. For more information: André Zimerman, MD, PhD, can be reached at andre.zimerman@hmv.org.br. Published by: Sources/Disclosures Source: Zimerman A, et al. Late breaker clinical abstracts. Presented at: European Atherosclerosis Society Congress; May 24-27, 2026; Athens, Greece. Disclosures: Zimerman reports receiving honoraria/expenses from Daiichi Sankyo, Eli Lilly and Novartis and serving on a consultant/advisory board for Novartis. Zimerman also reports that at the time of the trials, he was a member of the TIMI Study Group, which received institutional grant support through Brigham and Women’s Hospital from numerous drug and device companies including Ionis Pharmaceuticals. The CORE-TIMI 72a and CORE2-TIMI 72b trials were sponsored by Ionis Pharmaceuticals. Ask a clinical question and tap into Healio AI’s knowledge base. PubMed, enrolling/recruiting trials, guidelines Clinical Guidance, Healio CME, FDA news Healio’s exclusive daily news coverage of clinical data Learn more Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Source link

New Tech for Fertility Testing and Conception Support
Brittany Barreto, Ph.D., is a podcaster, an entrepreneur, and a molecular and human geneticist. (In other words, she’s really smart.) Read her column here each month to learn about what’s happening in the world of technology and innovation in women’s health. Trying to get pregnant can quickly become overwhelming. For many people, the process starts with a simple question, “Am I ovulating?” But fertility is far more complex than a single day on a calendar. Hormones fluctuate. Ovulation timing shifts. Sperm health matters. Cervical mucus changes. Stress, sleep and age can all play a role. Historically, understanding any of this required expensive clinic visits, bloodwork and a lot of waiting. Now, a new generation of fertility technology companies is bringing fertility tracking, hormone monitoring and conception support into the home. These tools are helping people gather more data about their bodies earlier in the fertility journey, sometimes before they ever set foot in a fertility clinic. Some are designed to identify fertile windows more accurately. Others confirm ovulation, monitor sperm health or support at-home insemination. Together, they reflect a broader shift in women’s health. Consumers increasingly want proactive, personalized health information they can access privately and conveniently. Here’s a look at the ways that technology is changing how people approach fertility today. 1. Fertility tracking is moving beyond calendar apps (Photo/courtesy Kegg) For years, fertility apps relied heavily on cycle averages and calendar predictions. But many people don’t ovulate exactly on day 14, and even people with “regular” cycles can experience significant variation month to month. That’s why many newer fertility tools focus on measuring biological signals directly rather than relying solely on predicted averages. One of those signals is cervical mucus. Kegg tracks cervical mucus changes linked to fertility Kegg offers an at-home fertility tracking device that measures changes in cervical mucus using vaginal sensor technology. Cervical mucus plays an important role in fertility. Most of the month, mucus acts as a protective barrier in the reproductive tract. But around ovulation, it changes consistency to help sperm survive and travel more effectively toward the egg. Research has shown that cervical mucus observations may predict fertility better than intercourse timing alone. The Kegg fertility tracker measures electrical changes in cervical mucus and provides users with daily fertility scores through an app. Research suggests that cervical mucus could be more accurate than classic basal body temperature for predicting ovulation. The tracker costs $477 but you can find sales that reduce it significantly. For example, it’s on sale for $279 right now. The Kegg tracker is FSA-/HSA-eligible and, at this time, guarantees pregnancy within 1 year of use or your money back. The device also reflects another major trend in fertility technology: the rise of longitudinal data collection. Instead of relying on a single hormone test or temperature reading, these systems gather daily data over time to personalize predictions for an individual user’s body. Wearable fertility trackers are turning body temperature into reproductive insights Another biological signal commonly used in fertility tracking is basal body temperature (BBT), which slightly rises after ovulation because of progesterone production. Historically, tracking BBT meant taking your temperature manually every morning before getting out of bed, something that can be difficult to do consistently. Now, wearable devices are automating that process. Femometer uses a smart ring to track fertility signals continuously Femometer continuously tracks body temperature, sleep, heart rate variability and other physiological metrics. The device is designed to help users identify and confirm ovulation while also monitoring broader health patterns, such as stress and sleep quality. Unlike many consumer wearables that were originally designed for fitness tracking, Femometer is a fertility-focused smart ring specifically marketed around reproductive health. The company says the ring’s predictive algorithm is based on data from over 10 million users over the last 10 years in business. Insurance doesn’t cover the ring, but it is HSA-/FSA-eligible and has a one-time fee ranging from $20 to $200, with no subscription required. Wearable fertility tracking is part of a broader movement toward passive health monitoring, technologies that continuously collect physiological data without requiring users to actively test every day. 2. Hormone testing at home is becoming more sophisticated (Photo/Courtesy Proov) Ovulation predictor kits have traditionally focused on luteinizing hormone (LH), which surges before ovulation. But fertility specialists have long known that multiple hormones influence fertility and implantation. New at-home hormone monitoring systems are expanding beyond LH alone. Proov measures four fertility-related hormones at home Proov offers an at-home testing system that measures four hormones associated with fertility: follicle-stimulating hormone (FSH), estrogen metabolites (E1G), LH and progesterone metabolites (PdG). Progesterone is especially important because it helps support implantation and early pregnancy after ovulation occurs. Many traditional ovulation tests can predict ovulation but cannot confirm whether progesterone levels rise appropriately afterward. Proov’s system combines urine test strips with smartphone-based analysis and personalized hormone reports. Unlike many traditional ovulation tests that only track LH surges, Proov measures multiple hormones throughout the cycle, including progesterone metabolites, to help confirm whether ovulation actually occurred. In a 2022 study, Proov Complete detected up to six fertile days by tracking across the menstrual cycle. Proov holds the distinction of being the first and only FDA-cleared at-home diagnostic test for confirming successful ovulation. The tests are available at major retailers, including CVS, Walgreens and Walmart, and most are FSA-/HSA-eligible. Costs are widely variable, depending on what you’re buying. They have individual tests starting at $14.99 and bundles that are as much as $500. The growing popularity of these tools reflects increasing consumer demand for deeper fertility insights without immediately escalating to expensive fertility workups. 3. At-home insemination is expanding reproductive options (Photo/Courtesy Mosie Baby) Fertility technology is also evolving beyond tracking and into direct support for conception. Mosie Baby brings FDA-cleared insemination into the home Mosie Baby created the first FDA-cleared at-home insemination kit available over the counter in the United States. The system includes specially designed collection cups and insemination syringes intended to improve comfort and sperm transfer compared to

Q&A: What clinical trials overlook when studying ultraprocessed foods
Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Key takeaways: Trials on ultraprocessed foods are often limited by their crossover design and control diets. Adjusting for nutritional factors like texture and high-calorie density may explain the effects of these foods. Randomized controlled trials may not properly capture ultraprocessed foods’ health effects due to their designs and limitations, experts suggest. In a commentary published in Science, Faidon Magkos, MSc, PhD, a professor of obesity and metabolism at University of Copenhagen in Denmark, and colleagues used five clinical trials in the United States, United Kingdom, Denmark and Japan to demonstrate their case. The findings of these trials on ultraprocessed foods (UPFs) “have been highly publicized and widely communicated, often in ways that suggest that ultraprocessing is inherently harmful to health.” “The design of these clinical trials, however, makes it very difficult to attribute the unfavorable effects of UPF-rich diets to ultraprocessing per se,” they wrote. “Instead, these effects are highly likely to be due to differences in traditional nutritional properties that frequently — but not uniformly — co-occur in UPFs.” Magkos and colleagues pointed out that all the trials used a crossover design, where the study participants were randomly given UPFs and non-UPF diets in an inpatient setting, outpatient setting or “through a combination of supervised and unsupervised eating.” “This ‘feeding’ trial design prevents confounding from varying diet adherence that occurs in ‘diet advice’ studies,” the authors wrote. Further, Magkos and colleagues said the minimally processed diets used in the studies “might not constitute appropriate controls, as they represent interventions of equal or greater intensity than UPF-rich diets.” They noted that the effects of UPFs in these studies are likely attributed to factors like texture and high saturated fat and salt amounts, which impact health “regardless of the degree of food processing.” As a result of the trials’ limitations, Magkos and colleagues said there is currently “weak support for an ultraprocessing-specific effect of UPFs on body weight regulation and cardiometabolic function that is independent of established nutritional determinants.” Healio spoke with Magkos about why nutritional variables are overlooked in these trials, how future dietary guidance could change amid weak evidence on UPFs, and more. Healio: Why are some of these important variables like food texture overlooked in trials? And how will incorporating these variables into future studies affect the outcomes? Magkos: Food texture, eating rate and calorie density are rarely measured because most nutrition trials are designed around nutrient content and nutritional composition of the diet, not the physical properties of foods (which is yet another important dimension of the diet, affected by multiple factors including preparation and cooking methods and level of food processing — but not necessarily “ultraprocessing”). Yet these variables strongly influence ad libitum energy intake and can fully account for the differences attributed to UPFs in these randomized trials. Incorporating them into future studies will allow us to separate the effects of ultraprocessing from the effects of energy density, texture, fiber and sodium contents, and so on — revealing whether ultraprocessing itself has any independent physiological impact. For the time being, this does not appear to be the case. Healio: If ultraprocessing is not the primary driver of negative health outcomes, what could explain the consistently observed associations between high UPF consumption and poor outcomes? Magkos: High UPF intake often co-occurs with diets that are calorie dense, low in fiber and protein, high in sodium and saturated fat, and dominated by soft, rapidly consumed foods. These nutritional and behavioral patterns — not the processing category — are well established drivers of weight gain and cardiometabolic risk. Observational studies capture these co-occurring features, so UPF intake becomes a proxy for overall dietary quality and eating behaviors rather than a causal driver in its own right. Healio: If future research shows that ultraprocessing itself has little effect on health, how would that change current dietary recommendations? Magkos: Most current dietary guidelines do not use UPF classifications, and rightfully so. However, they do suggest prioritizing whole and minimally processed foods whenever possible, and this recommendation should not change. Recommendations already emphasize nutritional quality — fiber, whole grains, unsaturated fats, lower sodium and limiting energy dense, nutrient poor foods. If future research confirms that ultraprocessing per se has little independent effect on health, it would reinforce the value of sticking with these established principles rather than adopting processing-based frameworks like NOVA. It would also help prevent well-intentioned but misleading messages that lump nutritionally sound foods together with clearly unhealthy ones. Recommendations should become more precise — encouraging people to choose foods that promote satiety, slow eating and lower energy density, regardless of whether they come with an “ultraprocessing” label. Healio: What advice should PCPs give to patients who are confused by conflicting messages about processed foods? Magkos: Tell patients that the goal is not to avoid all UPFs but to prioritize foods that are higher in fiber and protein, lower in energy density and harder in texture so they are slower to eat. Emphasize that texture, calorie density, and nutritional quality matter far more for weight and metabolic health than whether a food is classified as “ultraprocessed.” This reframes the conversation in practical, achievable terms and avoids the confusion created by broad processing labels. For more information: Faidon Magkos, MSc, PhD, can be reached at primarycare@healio.com. Sources/Disclosures Source: Healio Interviews References: Disclosures: Magkos reports receiving support from Arla Food for Health, Independent Research Fund Denmark, Novo Nordisk Foundation, and Sino-Danish Center for Education and Research. Please see the study for all other authors’ relevant financial disclosures. Ask a clinical question and tap into Healio AI’s knowledge base.

Mis ronchas crónicas seguían reapareciendo
English Tal como se relató a Erica Rimlinger Las ronchas se manifestaron por primera vez un poco después de cumplir 20 años tras usar una lavandería de autoservicio. Cuando estaba poniéndome prendas que acababa de lavar, se formaron ronchas que señalaban perfectamente la forma de mi sostén y ropa interior. Conmocionada y con mucha comezón, llamé a mi mamá, quien supuso que había usado mucho detergente cuando lavé la ropa o que tenía una reacción alérgica. Recomendó un antihistamínico, que no surtió ningún efecto en esa comezón que no paraba. Sin poder sentarme o tolerar que ropa toque mis ronchas rojas e inflamadas, llamé a la línea de asistencia de enfermería de mi seguro médico. Después de una hora de espera para que alguien me atienda, me dieron la autorización para que vaya a sus instalaciones de atención de urgencias. En ese lugar, un doctor me inyectó un corticosteroide y me recetó píldoras de corticosteroides para que los tome los días siguientes. Me dijo que siga tomando un antihistamínico y recomendó que no use esa marca de detergente otra vez. Se calmó el ardor de las intensas ronchas y su color cambió a rosado, y luego, después de aproximadamente una semana, desaparecieron. Pensé que este episodio fue una experiencia de la cual aprendería algo y que había terminado. Pero no fue así: Las ronchas se manifestaron otra vez. Cada vez, mis proveedores de atención médica y yo asumimos que algún alérgeno desconocido causaba estos episodios. Me daban un tratamiento de corticoesteroides, tomaba antihistamínicos y las ronchas desaparecían como por arte de magia la semana siguiente. No me importaba ningún efecto colateral de tomar los corticosteroides: Simplemente necesitaba que funcionen cuando los usaba. Mantenía registros detallados de lo que comía y lo que usaba en mi piel o cerca de ella. Tuve consultas con un alergólogo, quien no pudo encontrar la causa de los brotes. Cuando tenía entre 20 y 40 años, los brotes eran relativamente cortos, pero tenía que poner mi vida en pausa por una semana mientras lidiaba con ellos. La comezón era demasiado intensa para poder enfocarme en algo por mucho tiempo y ninguna crema, píldora ni tratamiento proporcionaba suficiente alivio. Después de cumplir 40 años, los episodios de ronchas fueron más largos y no desaparecían rápidamente con corticosteroides ni con varios antihistamínicos. Para entonces, los brotes duraban mucho más de una semana y se sentían inmanejables, por lo que estaba desesperada por encontrar algún alivio. Si imaginas que esas ronchas eran varios bultos pequeños, rojos y con comezón como picaduras de mosquitos, no comprendes la magnitud completa de lo que sentía. Mis ronchas brotaban en forma de dolorosas inflamaciones que no podían tocarse sin irritar mi cuerpo y sin empeorar la comezón aún más. Era como si alguien afeitase mi piel con una navaja y me cubriera con lana. Durante mis brotes, un raspón leve de una uña en mi piel se transformaba en una roncha. Podía escribir mi nombre con ronchas en mi piel, un fenómeno denominado dermografismo. En 2019 tuve un brote de ronchas que duró meses, es decir mis ronchas eran “crónicas“. Tal como me ocurría con brotes más cortos, era casi imposible trabajar, sentarme, o realizar actividades normales o simples tales como bañarme. Tenía ronchas todos los días y no sabía cuándo serían más graves o en qué lugar la inflamación y la comezón se manifestarían. La dolorosa comezón era abrumadora y nada podía calmarla. Durante los brotes, seguí documentando todos los detalles de mi vida, tratando de identificar cualquier causa que explicase la manifestación, desaparición, empeoramiento o alivio de los brotes. No pude identificar ningún patrón, alérgeno ni ninguna clave de por qué ocurría esto. Durante mi último brote, tampoco pude encontrar ninguna forma de alivio que funcione todavía. Hay muchos mitos relacionados con las ronchas crónicas y uno es que simplemente reducir el estrés elimina los brotes. Al igual que para muchas mujeres que experimentan enfermedades crónicas, me pasaba frecuentemente que el personal médico me decía que sí tenía más calma, no me enfermaría. Pero, las notas que tomaba en forma regular acerca de las circunstancias relacionadas con mis brotes indicaban que no los causaban mis emociones. Sentía que personas minimizaban lo que me pasaba cuando insinuaban que podía controlar la reacción física extrema de mi cuerpo simplemente reduciendo el estrés, como si eso fuese siquiera posible. CSU on Kristen’s legs Durante el brote de la primera semana de 2019 sentí la peor agonía que había experimentado en mi vida y entonces el brote se volvió completamente impredecible. No podía sentarme y quedarme quieta debido a la gravedad de la comezón. No me dejaba dormir, trabajar, socializar con amigos y familiares ni realizar actividades básicas. Después de unos días, las cosas mejoraron, pero las ronchas seguían presentes todos los días: primero durante semanas y luego meses. Hace un tiempo, me diagnosticaron un trastorno autoinmunitario llamado la enfermedad de Graves-Basedow. Me preguntaba si podía tener alguna relación con mis ronchas. Después de unas investigaciones y de unas consultas con mi inmunólogo, aprendí sobre la urticaria crónica (UC) o ronchas crónicas. En la mayoría de personas con este trastorno, su causa nunca se identifica, por lo que se denomina urticaria crónica espontánea (UCE), pero los brotes se asocian frecuentemente a problemas autoinmunitarios. Tomaba corticosteroides y dosis cuádruples de antihistamínicos que no proporcionaban alivio a largo plazo. Finalmente encontré una alergóloga e inmunóloga que sabe que la UCE casi nunca es una reacción alérgica, a pesar de las falsas creencias populares. Sabía lo que debía hacerse y me dio muchas esperanzas. Seguí tomando antihistamínicos y empecé a recibir un tratamiento que requiere una inyección en la parte posterior de cada brazo cada mes. Para el tercer mes, no había notado ninguna mejora. Llamé a un amigo que es un farmacólogo y le pregunté, “¿tendré que soportar esto siempre? ¿Por qué no puedo librarme de esto?” Mi amigo contactó a un colega en quien confía, experto en ese campo, que me dijo que siga

ACG cautions new CRC screening guideline may mislead patients
Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Key takeaways: A new American Cancer Society guideline has added recommendations for blood-based screening tests for CRC. The updated guidance may lead some patients to first choose lower-performing tests, ACG warned. ACG has issued a statement urging clinicians to interpret American Cancer Society’s revised colorectal cancer screening guidance with caution. In the statement, ACG expressed concern that the recommendation of blood-based tests for some patients risks undermining adherence to higher-sensitivity screening options. The new American Cancer Society (ACS) guidance reaffirms that adults at average risk for CRC should be screened between ages 45 and 75 years, but recommends blood-based tests as a “not preferred” option for patients who decline or do not complete stool-based screening or colonoscopy. “We want to ensure that the ACS guideline is implemented the way it was written,” ACG president William D. Chey, MD, MACG, AGAF, FACP, RFF, told Healio. “Gastroenterologists, as experts in CRC screening, will need to educate [patients] in ways that minimize substitution of colonoscopy or high-quality stool tests for the less accurate blood test.” There is a misconception among some patients that blood-based screening outperforms stool-based tests, as noted in an editorial accompanying the ACS guideline. “The diagnostic accuracy of Shield (Guardant Health) is lower than that of stool tests for early stage CRC and advanced polyps,” ACG Trustee Aasma Shaukat, MD, MPH, told Healio. Colonoscopy is estimated to detect more than 95% of colorectal cancers, according to ACG, as well as provide an opportunity to remove precancerous polyps. In contrast, ACG highlighted that a Shield test — which detects tumor DNA in the blood — misses 1 in 3 early-stage cases of CRC and 1 in 6 total cases. A study in The New England Journal of Medicine found the blood-based test had a sensitivity of 83.1% for CRC across all stages and a sensitivity of 55% for stage I CRC. Highlighting these statistics may help convey the efficacy of different screening options to patients, Chey said. When CRC is detected early, outcomes are dramatically improved — with 5-year survival rates exceeding 90%, according to an ACS press release issued with the guideline. However, around 1 in 3 eligible U.S. adults have not had recommended CRC screening. “ACG supports improving adherence to CRC screening among unscreened individuals,” the organization said in the statement. “However, we want to be certain that the unscreened individuals are given genuine opportunity to complete a ‘preferred’ test first, before being offered a blood test.” CMS this month announced it would cover noninvasive biomarker tests, with specific parameters, every 3 years for patients at average risk for CRC. Additionally, patients must be “provided with information about the test performance and the importance of a follow-on colonoscopy if the test returns a positive result.” In its statement, ACG also expressed concern that limited time during patient visits may lead to patients receiving incomplete information about CRC screening options. Specifically, ACG noted that clinicians may not have time to ensure patients are aware of the limitations of each, and that if they have a positive result from a blood or stool test, they still require a follow-up colonoscopy. “Gastroenterologists already understand the advantages and benefits of colonoscopy compared with blood-based tests,” Chey said. “As a broader pool of health care professionals begins to advise patients on CRC screening, it’s unlikely that every patient interaction will practically be able to cover the nuances of this guideline.” According to Shaukat, direct-to-consumer marketing may also contribute to misconceptions among patients, because “the main message that the blood test should be offered second line is lost.” Chey agreed but emphasized a big-picture concern. “Even if every headline and every clinician communicated all of the appropriate caution, this recommendation requires too much of patients,” Chey said. “Patients shouldn’t have to parse and process what it means to be ‘recommended’ but ‘not preferred.’” ACG encourages clinicians to “work with primary care colleagues and health systems to develop systems unique to each practice enabling colonoscopy and stool tests to be offered first line,” Shaukat told Healio. Shaukat recommends clinicians use a checklist when counseling patients to ensure they cover the benefits and limitations of each CRC screening test. She also suggests sharing educational materials with patients ahead of or during office visits. “Many Americans are learning about these tests for the first time,” Chey said. “We hope to assist patients that already have misconceptions and to appropriately inform patients before misconceptions can develop.” For more information: William D. Chey, MD, MACG, AGAF, FACP, RFF, is H. Marvin Pollard Professor of Gastroenterology, professor of nutrition sciences, and chief of the division of gastroenterology and hepatology at Michigan Medicine. He also is a Healio Gastroenterology Peer Perspective Board Member. He can be reached on X at @umfoodoc. Aasma Shaukat, MD, MPH, is Robert M. and Mary H. Glickman Professor of Medicine and director of outcomes research in the division of gastroenterology and hepatology at NYU Grossman School of Medicine. She can be reached at gastroenterology@healio.com. Published by: Sources/Disclosures Source: Press Release References: Disclosures: Chey reports consulting roles with Ardelyx, Atmo, Bausch Health, Biomerica, Blueprint Medicines, Gemelli Biotech, Phathom Pharmaceuticals, Takeda Pharmaceuticals, Vibrant and Viscera Labs; grant/research funding from Bausch Health, Commonwealth Diagnostics International, FDA and NIH; stock options in Coprata, Evinature, FoodMarble, Kiwi Biosciences and ModifyHealth; serving as a board member/on the advisory panel at ACG, GI Health Foundation, International Foundation for Gastrointestinal Disorders and Rome Foundation; and holding patents for Digital Manometry, My Nutrition Health and Rectal Expulsion Device. Shaukat reports consulting roles with Freenome, Geneoscopy and Universal Diagnostics. Ask a clinical question and

Why Do My Legs Hurt at Night? Causes & Relief for Burning
If you’re losing sleep because of burning, throbbing leg pain that intensifies at night, you’re not alone—and there are solutions that can help restore your rest and quality of life. Key Takeaways: Nighttime leg pain often worsens due to increased inflammation, reduced distraction, and horizontal positioning during sleep Common causes include sciatica, peripheral neuropathy, restless leg syndrome, and vascular issues Warning signs requiring prompt medical attention include sudden severe pain, swelling, redness, and leg pain with fever Conservative treatments include elevation, stretching, heat/cold therapy, and over-the-counter anti-inflammatories Interventional pain management techniques like nerve blocks and epidural steroid injections provide targeted relief for persistent nerve pain Pain Specialists of America offers comprehensive, minimally invasive treatments for nighttime leg pain along the I-35 corridor from Waco to Seguin When Bedtime Turns to Leg Pain Rather than Rest Leg pain at night can turn what should be restful sleep into hours of discomfort and frustration. Whether you’re experiencing burning sensations, sharp nerve pain, or throbbing discomfort that seems to intensify after dark, nighttime leg pain can significantly impact your quality of life. For many patients across Central Texas, this nightly suffering becomes a cycle that’s difficult to break. Understanding why leg pain often worsens at night is the first step toward finding relief. At Pain Specialists of America, we regularly help patients identify the underlying causes of their nighttime leg discomfort and develop personalized, comprehensive treatment plans that address the source of the pain—not just the symptoms. What is Nighttime Leg Pain? Nighttime leg pain refers to discomfort in the legs that occurs or intensifies during evening hours or while trying to sleep. This pain can present in various ways, including: Burning sensations that feel like heat or fire within the legs Sharp, shooting pains that travel down the leg Dull, aching discomfort that throbs persistently Cramping or tightening of leg muscles Tingling, “pins and needles,” or numbness Many patients describe their nighttime leg pain as more severe and disruptive than daytime discomfort. This isn’t your imagination—there are physiological reasons why leg pain often intensifies after dark. Why Does Leg Pain Get Worse at Night? Leg pain commonly intensifies during nighttime hours for several specific reasons: Increased inflammation: During the day, your body produces more cortisol, a natural anti-inflammatory hormone. At night, cortisol levels drop, potentially allowing inflammation to increase around irritated nerves or tissues. Fewer distractions: When you’re active during the day, your brain processes multiple inputs and may not focus as intently on pain signals. At night, with fewer distractions, your perception of pain may heighten. Horizontal positioning: Lying down changes fluid distribution in your body and can increase pressure on certain nerves or blood vessels. Temperature changes: Your body temperature naturally fluctuates throughout the day, with changes occurring at night that can influence nerve sensitivity and blood circulation. Body’s pain processing changes: Research suggests that pain perception actually changes during different times of the day, with many people experiencing heightened sensitivity in evening hours. Understanding these factors helps explain why treatments specifically targeting nighttime pain patterns can be particularly effective. Common Causes of Burning Leg Pain and Nerve Pain at Night Several conditions can cause or contribute to leg pain that worsens at night: Sciatica: When the sciatic nerve becomes compressed or irritated, it can cause burning, shooting pain that radiates from the lower back through the buttock and down the leg. This pain often intensifies when lying down as pressure on the nerve may increase. Peripheral Neuropathy: Often associated with diabetes, this nerve damage typically begins in the feet and legs, causing burning, tingling, or shooting pains that frequently worsen at night. Restless Legs Syndrome (RLS):This neurological disorder causes uncomfortable sensations in the legs and an irresistible urge to move them, particularly when resting or trying to sleep. Vascular Issues: Conditions like peripheral artery disease (reduced blood flow) or venous insufficiency (poor vein function) can cause leg pain that worsens when legs are elevated during sleep. Nocturnal Leg Cramps: These sudden, painful contractions of leg muscles often occur during sleep and may be related to dehydration, electrolyte imbalances, or muscle fatigue. Arthritis: Joint inflammation can cause throbbing leg pain that may feel worse at night due to increased inflammation and lack of movement. Radiculopathy: Nerve root compression in the spine can lead to radiating leg pain, similar to sciatica but potentially affecting different nerve pathways. Each of these pain conditions requires a specific approach to diagnosis and treatment, which is why consulting with pain management specialists is crucial for effective relief. How Does Interventional Pain Management Help with Nighttime Leg Pain? Interventional pain management offers targeted approaches to treating the specific causes of nighttime leg pain, particularly when it stems from nerve irritation or compression. These techniques work by: Directly targeting inflammation sources: Procedures like epidural steroid injections deliver anti-inflammatory medication precisely where nerve irritation occurs, reducing swelling and pain signals. Interrupting pain transmission: Nerve blocks temporarily prevent pain signals from reaching the brain, providing immediate relief while the body’s natural healing processes occur. Addressing underlying structural issues: Minimally invasive procedures can relieve pressure on compressed nerves caused by herniated discs or spinal stenosis. Providing long-term relief with minimal medication: By treating pain at its source, interventional techniques often reduce or eliminate the need for oral pain medications that can cause side effects or lose effectiveness over time. Complementing physical therapy and rehabilitation: Pain reduction from interventional procedures allows patients to participate more effectively in strengthening and mobility exercises that support long-term improvement. At Pain Specialists of America, our comprehensive approach to nighttime leg pain includes careful diagnosis, personalized treatment planning, and ongoing support to help you regain restful sleep and daytime function. Nighttime Leg Pain vs Other Nighttime Pain Conditions Understanding how nighttime leg pain differs from other nocturnal discomfort helps in proper diagnosis and treatment: Nighttime Leg Pain Restless Leg Syndrome Nocturnal Leg Cramps Fibromyalgia May include burning, shooting, or throbbing sensations Creates uncontrollable urge to move legs Involves sudden, intense muscle contractions Widespread pain throughout

Expert Answers: Questions and Answers about Eosinophilic Esophagitis (EoE)
Español June is Dysphagia Awareness Month. Eosinophilic esophagitis (EoE) is a condition that causes chronic inflammation in the esophagus. This inflammation results in symptoms like trouble swallowing, chest pain and food impaction (when food gets stuck in the esophagus). While there is no cure for EoE, there are effective treatments to control symptoms and keep the condition in check. Without treatment, EoE typically worsens. EoE is becoming more common, and can affect people of any age. We spoke with Evan S. Dellon, M.D., MPH, gastroenterologist, and professor of medicine and adjunct professor of epidemiology at the University of North Carolina Chapel Hill, to learn more about EoE symptoms, how to get help and treatment options. What symptoms of EoE should prompt you to go to the doctor? In adults and adolescents, the most typical symptom is trouble swallowing or food getting stuck. It’s important to note that food going down slowly or getting stuck is actually abnormal. Many people who ultimately are diagnosed with EoE don’t pay attention to this symptom at first. They might just avoid certain foods or chew more carefully until there’s a major issue. Don’t wait until that happens. Any trouble swallowing or getting food down really should be checked out. Some other gastrointestinal (GI) symptoms, like chest discomfort or heartburn, are also associated with EoE. Other medical conditions can cause food to go down slowly or stick. When these symptoms happen along with asthma or eczema or food allergies, it’s more likely to be a sign of EoE. Children with EoE have totally different symptoms. It could be abdominal pain, vomiting, poor growth, failure to move to different consistencies or food avoidance. Many pediatric GI conditions can cause those symptoms. But they could also be signs of EoE, especially if a child also has eczema, asthma or food allergies as well. If you have EoE, why is getting diagnosed so important? We think that EoE generally starts as allergic inflammation. Over time, if left untreated, that inflammation can progress to scar tissue. Then the esophagus can become narrow and stiff, causing more symptoms and complications like food impaction. Food impaction can lead to a perforation or a rupture of the esophagus, a very severe problem. It doesn’t happen frequently, but these are the complications we worry about. Kids who are affected severely may become malnourished. There’s also an impact on quality of life. Anything that impacts your eating will affect social events, family gatherings, work events and travel and can cause significant anxiety. The symptoms, the impact on quality of life and the potential complications are good reasons to get checked out. How do you get an EoE diagnosis? The diagnostic process comes down to an endoscopy to look into the esophagus. We don’t have any blood tests or other ways to diagnose EoE. The endoscopy is a sedated procedure. A lighted camera goes into the mouth and down into the esophagus and stomach. We look for typical signs of EOE. The esophagus can look swollen. It can be coated with white spots, which is inflammation. There can be scar tissue like rings or strictures. We send a biopsy to a pathologist who examines the allergy cells, which are the eosinophils. If there are enough eosinophils, and we can eliminate other things that might cause them, we can formally diagnose EoE. Why is it important to have continuous care if you have EoE? EoE is a chronic condition that needs to be managed over time. If people are diagnosed but not treated, many will ultimately develop more severe complications. It’s important to have a team in place and be consistent with treatment. There’s a range of severity with the condition. The team will customize the approach for each person’s situation. Someone who has been to the emergency room with an impaction, for example, will be followed much more closely than someone with mild symptoms. Continuous care is different for every person, but it’s very important to have it in place to avoid flare-ups and worsening problems. What types of healthcare providers should be part of your care team if you have EoE? Some people will be followed primarily by GI doctors. Some people will follow primarily with allergists. Some people may follow with both in more of a multidisciplinary fashion. Children may also need feeding therapists and other multidisciplinary providers. We often work with dieticians or nutritionists. How do you manage EoE? There are two major treatment categories: Diet elimination and medication. We think that EoE is a food-triggered condition for most patients. Unlike a typical food allergy, with an immediate reaction, it’s a condition where eating certain foods over a long period of time triggers inflammation. Current allergy tests are not really accurate for EoE, so it’s a little tricky. But we do know the most common food triggers: dairy, wheat, eggs, soy, nuts and seafood. Elimination diets can be used to identify food triggers and remove them from the diet. It’s a good option, but it really depends on the individual patient. Anti-acid medicines such as omeprazole (Prilosec) or lanzoprazole (Prevacid) are often the first medicine we try. Around 30%–40% of people may respond to these simple medicines. Then there’s a topical steroid. We now have an approved medication, budesonide oral suspension (Eohilia), that’s specifically formulated to stick in the esophagus. It can be effective in 50%–60% of people, if not more. Another we use is dupilumab (Dupixent), a systemic medicine. It’s a weekly injection that blocks some of the allergy factors that cause EoE. Typically it’s reserved for people who aren’t responding to other treatments. It might also be used for people being treated for asthma and eczema as well as EoE because dupilumab is approved for all of them. Why is management of EoE a lifelong process? The vast majority of people can get EoE under control, but it is chronic. If people are not treated, they tend to have issues down the road. Not everyone will have complications, but


