

October 28, 2026 2 min read Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Key takeaways: Jennifer A. Shuford, MD, said she wants to spend more time with family. Reports said she has disagreed with the administration’s stance on vaccines. Jennifer A. Shuford, MD, MPH, resigned as the CDC’s deputy director and chief medical officer after spending just 4 months at the agency. Shuford said she was leaving to spend more time with her family. “I am so thankful to President Trump and Secretary Kennedy for giving me the opportunity to help lead CDC,” she said in a statement provided to Healio. “It has been an amazing experience, and I will be forever grateful for it.” The CDC announced that Jennifer Shuford, MD, resigned from her high-ranking dual role at the agency. T he Washington Post first reported Shuford’s departure. Two anonymous sources told the Post that disagreements over the Trump administration’s vaccine policies factored into her decision to exit the agency. Shuford’s departure comes amid the largest surge in measles cases in the United States since 1991, according to the CDC. During Shuford’s brief stint, the administration continued its efforts to overhaul the childhood immunization schedule and make changes to the MMR vaccine, drawing sharp criticism from public health officials. Satish K. Pillai, MD, MPH, will fill Shuford’s dual role at the CDC on an interim basis, HHS confirmed to Healio. Pillai led the agency’s initial Ebola response in the Democratic Republic of Congo earlier this year but stepped down from that position in late July. HHS said it will begin a search for a permanent successor “in the near future” but did not specify a timeline on when that decision could be made. In a statement, CDC director Erica Schwartz, MD, JD, MPH, commended Shuford’s “outstanding leadership and commitment to the CDC and public health, especially as she has navigated an exceptionally demanding, high-profile, and constantly evolving environment over the past several months.” Anne Schuchat, MD, former principal deputy director and two-time acting director of the CDC, told Healio that the agency will miss Shuford’s veteran public health leadership. “It is always hard to know what may underpin a senior leader’s decision to step down, so I would not want to speculate,” Schuchat said. “But I can say that I had heard that Dr. Shuford was much appreciated by career staff who felt she had brought important state public health experience to the agency’s senior leadership. So, from that perspective it is certainly a loss.” Shuford, whose last day is scheduled for Nov. 12, stepped into her dual role at the CDC in June. She had previously served as the commissioner of the Texas Department of Health and Human Services from 2022 to 2026, leading the state’s response to a measles outbreak in West Texas. For more information: Anne Schuchat, MD, can be reached at infectiousdisease@healio.com. Published by: Sources/Disclosures Source: Healio Interviews References: Disclosures: Schuchat report no relevant financial disclosures. Ask a clinical question and tap into Healio AI’s knowledge base. PubMed, enrolling/recruiting trials, guidelines Clinical Guidance, Healio CME, FDA news Healio’s exclusive daily news coverage of clinical data Learn more Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Source link
Excessive bloating, gas consistent burden for menopausal women, study shows
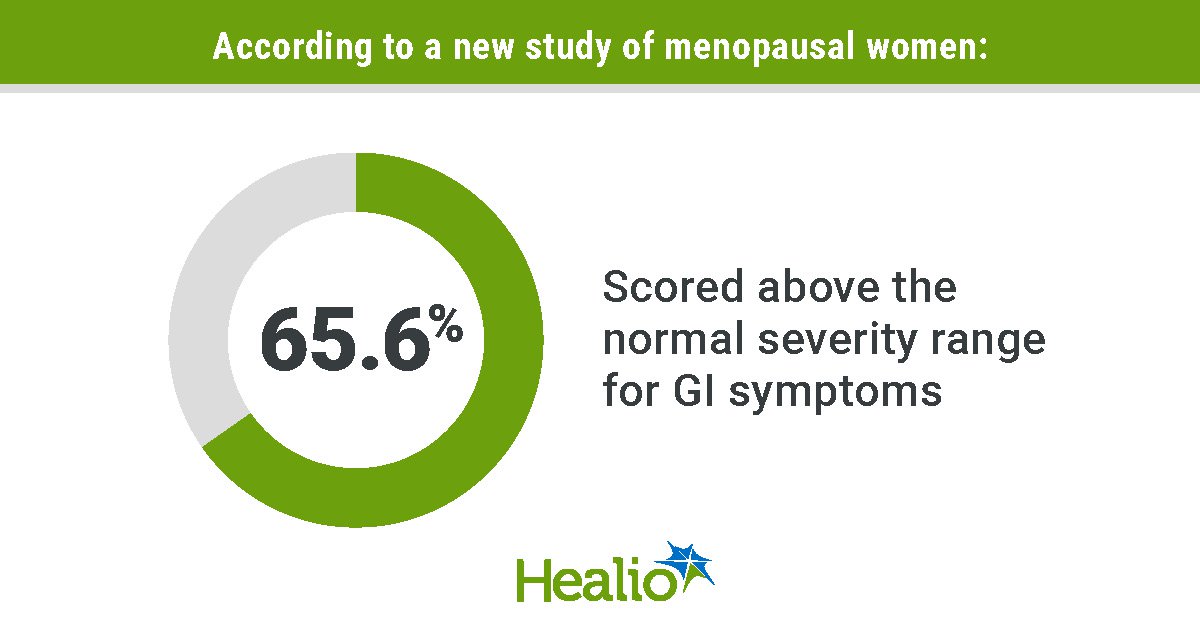
October 28, 2026 2 min read Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Key takeaways: Over 65% of women in one of the three phases of menopause have bloating and gas above the normal severity range. In the study’s next steps, researchers will look at the correlation between GI symptoms and anxiety. Excessive bloating and gas are prevalent gastrointestinal symptoms in women throughout the menopause trajectory, with 65.6% of participants in a new study scoring above the normal severity range. The study, conducted by a research team at the University of Calgary in Alberta, Canada, is aimed at better understanding the relationship between GI issues and anxiety for women in premenopause, perimenopause and postmenopause. “Essentially, [menopausal women] have more severe bloating and gas compared with the normal value that we usually consider,” Sanjana Solomon, the study’s lead author, told Healio. “This was prevalent across all stages, meaning it included premenopause, perimenopause, and postmenopause, so this is something that is seen throughout and not just in a particular stage.” The study included a cohort of 1,832 women aged 40 to 60 years and were premenopausal to postmenopausal. Participants filled out self-reported questionnaires, provided stool and blood samples, underwent physical and cognitive assessments, and participated in qualitative interviews. The researchers analyzed the GI burden in the women and found that 65.6% scored above the normal severity range for bloating and gas, and this result was consistent throughout the menopause trajectory. They found that significantly fewer women scored above the normal range for other GI symptoms like constipation (23.3% above normal), diarrhea (13.6%), pain (19.6%) and nausea (10.2%). Researchers also analyzed anxiety scores in the women, finding that 17.5% of the participants reported moderate to severe anxiety. The study showed that 14.6% of those women were in premenopause, and the prevalence of anxiety rose to around 19% during perimenopause and postmenopause. This is the first phase of a multiyear study to further examine the association of GI symptoms and anxiety in the women in the cohort, according to Solomon. “We hope to bring them in over the subsequent years to repeat these tests to understand how these changes occur in them individually long term and be able to make broader conclusions from that,” Solomon said, noting that is study is meant to establish a “baseline.” The researchers believe there needs to be more investigation to fully understand the underlying mechanisms for GI symptoms and anxiety. The cohort is currently in its second year of testing, and the research team will continue its analysis by investigating the gut microbiota profiles of the study’s participants. “We are trying to understand if these more severe gut symptoms are potentially attributed to more anxiety, or if more anxiety in individuals causes these bloating and gut symptoms,” Solomon said. For more information: Sanjana Solomon can be reached at primarycare@healio.com. Sources/Disclosures Source: Solomon S, et al. Gastrointestinal symptoms are associated with anxiety across the menopause trajectory: Findings from the MOMENTUM Canadian menopause cohort. Presented at: Annual Meeting of the Menopause Society; Oct. 20-24; 2026; San Diego. Disclosures: Solomon reports funding from the Joan Synder Fund for Excellence in Kinesiology Research and the Canadian Institutes of Health Research. Ask a clinical question and tap into Healio AI’s knowledge base. PubMed, enrolling/recruiting trials, guidelines Clinical Guidance, Healio CME, FDA news Healio’s exclusive daily news coverage of clinical data Learn more Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Source link

Saroglitazar favors US patients for PBC response, pruritus relief
October 28, 2026 2 min read Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Key takeaways: Saroglitazar showed superior biochemical and pruritus response in U.S. vs. non-U.S. patients with PBC. ALP normalization rates were similar between groups despite greater ALP reductions in U.S. patients. NASHVILLE, Tenn. — Patients in the U.S. with primary biliary cholangitis exhibited greater biochemical response and improvement in pruritus with saroglitazar magnesium than non-U.S. patients, according to data presented here. Despite slightly higher baseline liver enzyme levels for U.S. patients, alkaline phosphatase normalization rates were similar between U.S. and non-U.S. groups. Raj K. Vuppalanchi, MD, FACG, speaks at the podium during ACG Annual Scientific Meeting. Photo: Robert Stott. “Saroglitazar is PPAR-alpha/gamma agonist with an interesting targeting pathway in the pathogenesis of PBC,” Raj K. Vuppalanchi, MD, FACG, director of hepatology at Indiana University School of Medicine, told attendees at ACG Annual Scientific Meeting. “[Saroglitazar primarily acts] as a PPAR-alpha agonist [which] results in beneficial effects through bile acid homeostasis and decreasing cholestatic inflammation. It also has a modest PPAR-gamma effect, which results in potential benefits through anti-inflammatory and possibly antifibrotic effects.” In findings from the phase 2b/3 EPICS-III trial presented at EASL Congress earlier this year, Vuppalanchi and colleagues reported that saroglitazar 1 mg (Zydus Therapeutics) significantly improved biochemical response in patients with PBC. At week 52, 56.7% of patients receiving saroglitazar achieved the primary endpoint, compared with 9.8% on placebo. Complete ALP normalization, the key secondary endpoint, was achieved by 8.2% of patients treated with saroglitazar vs. none who received placebo (P = .016). “To see if patients in the United States have consistent treatment response compared to the rest of the world,” Vuppalanchi and colleagues conducted a post hoc analysis of the EPIC-III trial. The researchers compared outcomes among 42 participants in the U.S. — 28 randomly assigned to saroglitazar and 14 to placebo — with those from 106 participants from outside the U.S., including 69 who received saroglitazar and 37 who received placebo. Baseline demographic and disease characteristics were generally comparable between the regional subgroups, although median baseline ALP was slightly higher among participants in the U.S. compared with non-U.S. participants (302 U/L vs. 287 U/L). At week 52, saroglitazar outperformed placebo for composite biochemical response among both U.S. and non-U.S. participants, with a greater placebo-adjusted treatment difference reported in the U.S. subgroup (60.7% vs. 41.6%). “The primary endpoint that we saw was that composite biochemical response favors saroglitazar in both the U.S. and non-U.S. regions, but the larger treatment difference was seen in the U.S. population,” Vuppalanchi said. At week 52, saroglitazar produced a greater mean reduction in ALP among participants in the U.S. vs. those outside the U.S. (–166.2 U/L vs. –104.7 U/L). However, ALP normalization rates were similar between the subgroups (7.1% vs. 8.7%). At week 24, the treatment difference in 5-D itch score also demonstrated a greater reduction in the U.S. subgroup (–4.4 vs. –2.8). “This exploratory regional analysis of the EPICS-III trial shows saroglitazar favored over placebo in both U.S. and non-U.S. populations, but the treatment differences in the U.S. population were numerically higher compared to the non-U.S. population,” Vuppalanchi said. “Although ALP normalization rates were similar, the treatment differences in the 5-D itch score also appeared to be higher in the U.S. subgroup, and saroglitazar was well tolerated and demonstrated a great safety profile.” Published by: Sources/Disclosures Source: Vuppalanchi RK, et al. Greater treatment response to saroglitazar in US versus non-US patients with primary biliary cholangitis: A geographic subgroup analysis of the phase 3 EPICS-III trial. Presented at: ACG Annual Scientific Meeting; Oct 12-14, 2026; Nashville, Tenn. (hybrid meeting). Disclosures: Vuppalanchi reports an advisory board role with and grant/research support from Takeda Pharmaceuticals and grant/research support from Eli Lilly & Co. and Zydus Therapeutics. Please see the study for all other authors’ relevant financial disclosures. Ask a clinical question and tap into Healio AI’s knowledge base. PubMed, enrolling/recruiting trials, guidelines Clinical Guidance, Healio CME, FDA news Healio’s exclusive daily news coverage of clinical data Learn more Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Source link

Viral hepatitis in pregnancy: Updated guidelines for HBV, antivirals for HCV
October 28, 2026 2 min watch Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio NASHVILLE — In this Healio video, Tatyana Kushner, MD, MSCE, discusses a presentation from the GI Ignite session about viral hepatitis in pregnancy at the ACG Annual Meeting. “It’s an exciting time for viral hepatitis in pregnancy,” Kushner, associate professor of medicine and director of outcomes clinical research in the division of gastroenterology and hepatology at Weill Cornell Medicine, told Healio. In the early morning session, experts talked about updated guidelines from AASLD/IDSA for hepatitis B and hepatitis C treatment with antivirals in pregnancy. Published by: Sources/Disclosures Source: Healio Interviews Disclosures: Kushner reports no relevant financial disclosures. Ask a clinical question and tap into Healio AI’s knowledge base. PubMed, enrolling/recruiting trials, guidelines Clinical Guidance, Healio CME, FDA news Healio’s exclusive daily news coverage of clinical data Learn more Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Source link

Sorting through ‘fact and fiction’: Natural supplements for MASH on TikTok
October 27, 2026 3 min watch Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio NASHVILLE — In this Healio video, Elliot Tapper, MD, FAASLD, discusses a presentation from the ACG Annual Meeting about popular supplements that are promoted on TikTok as treatments for MASH. “Come from a place of empathy, understanding that [both you and the patient] share the same goals. You want them to be healthy and happy, and you don’t want them to feel shame or to be less forthright with information about what they’re taking,” Tapper, a professor of medicine at the University of Michigan, told Healio. “And where you don’t know the answer, it’s okay to see how things play out in a time-limited trial with monitoring of liver enzymes and the like.” Published by: Sources/Disclosures Source: Barritt SA. TikTok Hepatitis: Popular supplements for MASH and their effects on the liver. Presented at: the ACG Annual Scientific Meeting; Oct. 9-14, 2026; Nashville. Disclosures: Tapper reports no relevant financial disclosures. Ask a clinical question and tap into Healio AI’s knowledge base. PubMed, enrolling/recruiting trials, guidelines Clinical Guidance, Healio CME, FDA news Healio’s exclusive daily news coverage of clinical data Learn more Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Source link

Medicaid expansion failed to lower IBD mortality
October 27, 2026 2 min read Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Key takeaways: Medicaid expansion did not markedly lower IBD mortality, despite a smaller increase in expansion states. Improved specialist access and biologic drug availability may be needed to reduce IBD mortality. NASHVILLE, Tenn. — Medicaid expansion did not appear to reduce inflammatory bowel disease-specific mortality over a 26-year period, according to a presenter at ACG Annual Scientific Meeting. However, researchers noted these findings should not minimize the benefits Medicaid coverage provides patients with IBD. “What stood out to me was the importance of interpreting that result within the outcome we measured,” Daniyal Raza, MD, assistant professor of medicine at LSU Health Shreveport, told Healio. “Mortality is a consequential endpoint, but it captures only one part of living with IBD. Our study does not tell us whether patients experienced better symptom control, fewer hospitalizations, more consistent treatment or improved quality of life. “A null mortality finding is not a comprehensive verdict on the value of insurance coverage,” he added. Raza and colleagues conducted a retrospective, state-level difference-in-differences (DiD) analysis to determine whether Medicaid expansion was linked to change in IBD-related mortality over time. They used CDC death certificate data attributed to Crohn’s disease or ulcerative colitis and included all ages in the analysis. “The question grew out of a practical concern: Patients with IBD need sustained access to care, but obtaining insurance does not necessarily end the difficulties they face getting treatment,” Raza said. “Prior authorization denials, appeals and delays in starting medications can remain obstacles.” Analysis included 21 states, which were grouped by those that expanded Medicaid coverage by January 2016 (n = 14) and those that had not through 2024 (n = 7). The researchers compared mean age-adjusted IBD mortality per 100,000 deaths between the two groups prior to expansion (1999-2013) and after expansion (2017-2024), excluding years 2014 to 2016 to allow for stabilization in Medicaid enrollment and use. Results showed states that expanded Medicaid coverage had a smaller increase in IBD mortality compared with states that did not expand coverage (relative change, +1% vs. +4.9%), but the difference was not statistically significant (DiD = 0.005; 95% CI, –0.022 to 0.031). A secondary analysis of individuals aged 15 to 64 years, using data pooled from 2007 to 2013 and from 2018 to 2024, also showed a smaller increase in IBD mortality in expansion states (+1.2% vs. +17.5%), which did not reach statistical significance. The researchers acknowledged study limitations, including use of state-level data rather than patient-level data, and differences in pre-expansion trends. “Our study did not demonstrate a mortality difference associated with Medicaid expansion, but it should not be interpreted as evidence that coverage is unimportant,” Raza told Healio. “For GI practices, the practical focus remains identifying where care gets interrupted: an authorization awaiting approval, an unaffordable prescription or difficulty arranging follow-up. “The question I would bring back to clinic is: Once a patient has coverage, what is still preventing them from receiving effective care?” he added. For more information: Daniyal Raza, MD, can be reached at daniyal.raza@lsuhs.edu. Published by: Sources/Disclosures Source: Raza D, et al. Medicaid expansion and IBD mortality: A state-level difference-in-differences analysis, 1999-2024. Presented at: ACG Annual Scientific Meeting; Oct. 12-14, 2026; Nashville, Tenn. (hybrid meeting). Disclosures: Raza reports no relevant financial disclosures. Please see the study for all other authors’ relevant financial disclosures. Ask a clinical question and tap into Healio AI’s knowledge base. PubMed, enrolling/recruiting trials, guidelines Clinical Guidance, Healio CME, FDA news Healio’s exclusive daily news coverage of clinical data Learn more Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Source link

Factores de riesgo de enfermedades cardiacas que podrías no conocer
ESTADÍSTICAS: En lo que se refiere a mujeres de 20 años o más, casi la mitad viven con enfermedades cardiovasculares y algunas no lo saben. ¿Cuáles son los factores de riesgo menos conocidos de enfermedades cardiovasculares (ECV)? o Estrés crónico puede causar inflamación, lo que puede contribuir con hipertensión y menores niveles de colesterol LAD “bueno”. o Tu cuerpo se repara en la noche y déficits de sueño pueden incrementar el riesgo de ECV y accidentes cerebrovasculares. o Interrupciones del sueño por apnea del sueño pueden causar hipertensión, grasa abdominal y latidos irregulares. o Bacterias GI útiles descomponen ciertos alimentos pero demasiadas bacterias “malas” en tu microbioma intestinal podrían causar que hayan más productos derivados perjudiciales para el colesterol y para los vasos sanguíneos. o Personas que reportaron aislamiento social y soledad tuvieron un riesgo 29% mayor de acontecimientos cardiacos y un riesgo 32% mayor de accidentes cerebrovasculares. o La glándula tiroidea juega un papel clave en la salud cardiaca y vascular. Personas con disfunción tiroidea pueden tener más ECV, incluyendo fibrilación auricular y niveles altos de colesterol. o Complicaciones cardiovasculares relacionadas con el embarazo, tales como nacimientos prematuros, preeclampsia e hipertensión durante el embarazo, ocurren en 1 de cada 7 mujeres, lo cual puede incrementar el riesgo de accidentes cerebrovasculares y de insuficiencia cardiaca después del embarazo. o La menstruación usualmente empieza entre los 10 y 15 años. Para mujeres que no se encuentran en ese rango, el riesgo de ECV aumenta. o Menopausia temprana: Asimismo, si dejaste de tener períodos menstruales temprano debido a algo como una remoción quirúrgica de los ovarios, la salud cardiaca puede verse afectada. Las mujeres que empiezan con la menopausia antes de los 40 años tienen un riesgo 40% mayor de cardiopatías coronarias. o Tratamientos oncológicos: Tratamientos vitales tales como quimioterapias y radioterapias pueden tener efectos colaterales negativos, denominados cardiotoxicidad, los cuales pueden persistir después de tratamientos oncológicos. o La salud oral: No se sabe concluyentemente si hay una conexión directa entre la salud oral y cardiaca, pero hay una correlación entre personas con enfermedades periodontales y cardiopatías coronarias e hipertensión, posiblemente debido a inflamación o a bacterias nocivas en las encías que llegan a los vasos sanguíneos. La población a la que perteneces puede predecir tu riesgo de ECV – Las tasas de hipertensión varían por raza. En un análisis, el 59% de adultos de raza negra tenían hipertensión, esa tasa era menos del 45% para adultos hispanos, de raza blanca y asiáticos. – Personas desempleadas tienen un riesgo 84% mayor de acontecimientos cardíacos peligrosos y casi 3 veces más riesgo de muerte en comparación con personas que tienen empleo. – Personas con bajos ingresos con hipertensión tienen un mayor riesgo de mortalidad que otras personas con hipertensión. ¿Qué puedes hacer? 1. Pide a tu profesional clínico que se hagan pruebas referenciales para conocer el funcionamiento de tu corazón. Si las pruebas descubren un problema, te podrían prescribir medicamentos, cambios de tu estilo de vida u otro tipo de intervenciones. 2. Si tienes cáncer, haz que un cardiooncólogo forme parte de tu equipo de especialistas para que puedas seguir recibiendo tu tratamiento mientras proteges tu corazón.3. Programa consultas dentales en forma regular y cepilla y limpia tus dientes con hilo dental en forma regular. 4. Identifica lo que puedes cambiar y lo que no. Haz cosas pequeñas todos los días que sean beneficiosas para tu corazón. Reúnete con amigos para caminar y come algo saludable después de eso. Este recurso educativo se preparó con el apoyo de Merck. Source link

Preguntas que deberías hacer a tu profesional clínico sobre la enfermedad de Alzheimer
Incluso si sospechas que podrías tener la enfermedad de Alzheimer, escuchar el diagnóstico podría ser difícil. Sin embargo, todavía puedes controlar ciertos aspectos de tu atención sabiendo lo más posible. Esto implica hacer incluso más preguntas, las cuales podrían ser, entre otras: ¿Quién me tratará? ¿Qué cambios podría anticipar en el futuro? ¿Hay algún tratamiento que podría ser útil para retrasar el progreso de la enfermedad? ¿Soy elegible para los tratamientos? ¿Hay algún tratamiento para mis síntomas? ¿Hay algún ensayo clínico para el cual podría ser elegible? ¿Debería implementar algún cambio de mi estilo de vida, tal como dieta y ejercicio, que fomente mi salud general y posiblemente también sea útil para retrasar el progreso de la enfermedad? ¿Qué recursos hay para mí y para las personas que me cuidan? ¿Qué decisiones debería tomar ahora, tales como instrucciones previas o poderes notariales? ¿Puedo seguir conduciendo sin peligro? ¿Qué tipo de asistencia podría necesitar si quiero seguir viviendo en mi hogar? ¿Cuáles son los siguientes pasos que debería tomar? Podría ser difícil para algunas personas recibir atención para la demencia debido a su costo, la situación de su seguro, barreras lingüísticas y su ubicación geográfica. Si tienes algún obstáculo, pregunta a tu profesional clínico si hay sistemas de asistencia para ti, tales como servicios de bajo costo, opciones de transporte, servicios de intérpretes o programas de asistencia locales. Si vives sola y no tienes familiares o amigos que puedan ayudar a cuidarte, es particularmente importante que preguntes qué tipos de recursos hay y cómo obtener acceso a ellos. Esto podría incluir un trabajador social o un coordinador de atención médica para empezar. Podrías ser elegible para servicios comunitarios, tales como los que puedes encontrar en Eldercare Locator, parte de la Administración para la Vida Comunitaria del HHS [Departamento de Salud y Servicios Humanos]. La línea de asistencia, que funciona las 24 horas del día, los 7 días de la semana, de Alzheimer’s Association (1-800-272-3900) también podría ser útil. Source link

Questions to Ask About Complicated UTI Symptoms
When learning about cUTIs, you might come across words and terms you don’t know. Here is a list of some of the more common ones you might encounter: Antibiotic: Medication that kills bacteria to stop them from growing; used to treat bacterial infections Antimicrobial resistance (AMR): When germs such as bacteria or fungi change (mutate), they may resist drugs that used to kill them or keep them from multiplying. This is called AMR. Bacteria: Very small (single-cell) organisms, invisible to the naked eye Bladder: The hollow, spherical organ that holds urine until you pee Bloodstream infection: Infection in the blood Catheter-associated urinary tract infection (CAUTI): A UTI related to having or using a urinary catheter is called a CAUTI Complicated urinary tract infection (cUTI): A UTI with symptoms that suggest that it has spread beyond the bladder, including fever and pyelonephritis (kidney infection) Cystitis: Inflammation of the bladder, often caused by a bladder infection Dysuria: Discomfort, pain or burning when peeing Flank pain: Pain in the side of the body between your ribs and hip Hematuria: Red blood cells (blood) in your urine Lower urinary tract: The part of the urinary tract that includes your bladder and urethra (the tube that carries urine out of your body) Pyelonephritis: A kidney infection Recurrent UTI: UTIs that happen two or more times within six months or three times in a year. Recurrent UTIs aren’t necessarily cUTIs. Also called chronic UTIs. Sepsis: The body’s extreme reaction to an infection; a life-threatening emergency Systemic symptoms: These are symptoms that affect more than one part of your body beyond your bladder. These include fever, chills, low blood pressure or feeling very unwell. Upper urinary tract: This part of the urinary tract includes your kidneys and the ureters (tubes that bring urine from your kidney to the bladder) Urinalysis: A test that examines urine for different substances, including blood and the presence of bacteria. It can’t tell what type of bacteria is present, however. Urinary catheter: A thin, flexible rubber or plastic tube inserted through your urethra to the bladder that allows urine to drain Urinary frequency: Needing to pee more often than usual (more than seven times in a 24-hour period) Urinary incontinence: Accidental or unintentional release of urine, loss of bladder control Urinary retention: The inability to empty your bladder completely Urinary urgency: The very strong, sudden need to pee Urine culture: A urine test that identifies bacteria and other germs in the urine. If bacteria are found, testing can show what types of antibiotics are most likely to work. Source link
Facts About Rheumatoid Arthritis – HealthyWomen
While treatments such as medications and surgery help manage RA symptoms, there are things you can do at home as well. Low-impact physical activity like walking or swimming helps to increase or maintain muscle strength around joints. Doing repetitive movements like deep bending at the knees can cause joint injuries, so avoid them as much as possible. An anti-inflammatory diet (similar to the Mediterranean diet) might help reduce inflammation in joints and lower the risk of heart disease for people with RA. This includes unprocessed foods, fruits and vegetables, omega-3 fatty acids, whole grains, and reduced sugar. Maintain a healthy weight, which can decrease inflammation and pain, and if you smoke, try to quit. While you may not be able to fully prevent RA, you can take steps to reduce the risk. By beginning treatment right away, you can decrease the long-term damage to joints and help control swelling and pain. Source link


