

If you purchase an independently reviewed product or service through a link on our website, SheKnows may receive an affiliate commission. OK friends, when you think of porn, are you immediately turned off? Yeah, we hear that. It’s 2026, and yet it’s still not an easy task to find porn that you actually want to watch, meaning a website featuring hot, actually good porn that doesn’t overwhelmingly prioritize the male gaze or the male orgasm. Sure, you can wade through the videos to find one where female pleasure and (over-the-top-slash-faked) female orgasms are the focus — but even then, there’s the distinct feeling that because of the way she’s being filmed, there is still a man calling the shots. Let’s be honest, even if you’re watching it with a male partner, you may get the sense that the porn you’re trying to enjoy isn’t for you. And that can make it harder to lose yourself in the story or the sensations the way you’d want to. Related story A Scary Amount of Young People Are Going to Porn & Google for Sex Ed In other words: where are the porn sites that cater to the female gaze, that honor female sexuality in all its beautiful forms and that don’t objectify women in a way that will have you itching to take a shower immediately after viewing (in a bad way)? Where are the porn sites that feel current and up to date with what we want from sexual media today? There are good reasons these kinds of porn are necessary, too. Porn that honors female sexuality “allows us to actually see content that was designed for us with our pleasure in mind,” Gigi Engle, a certified sex and relationship psychotherapist and resident intimacy expert at dating app, 3Fun, tells SheKnows. “This can be pretty revolutionary as most of mainstream porn is made by men for men — which can really take us out of it because it doesn’t center things we actually want to see. Seeing lots of different female-centered sex acts, a range of bodies, and lots of pleasure can help us feel better about our bodies, our pleasure, and ourselves in general.” If that’s the kind of porn you’re itching for, fear no more, because we’ve found some legitimately great porn sites for you, the modern, self-loving woman. If you’re tired of porn that feels overwhelmingly straight and cis-male-centric, you’ll be pleasantly surprised by the following selection of sites. And while we’re at it, it’s probably the right time to treat yourself to some new sex toys to really turn up the heat (our current fave is the LELO’s new Sona 3 Cruise, FYI). Quick PSA, though: please take care and don’t browse this one at your desk, because you’ll be able to access some NSFW websites from here on out. Click with caution and when it’s time for You-time, have fun! And as Engle reminds us, support these ethical porn sites by “always, always, always pay[ing] for your porn!” A version of this story was published on April 2018. Quinn Image Credit: SheKnows Audio erotica stays a fave for erotic content, and while it’s not the same as visual porn, it is something you can get off to knowing it’s made ethically and with your tastes in mind. Quinn, for example, is particularly cool with its super user-friendly interface, cast of sensual and totally dreamy voices, and curated, inclusive playlists to hit all of your tastes. And if audio erotica is hitting all the right buttons for you, try out our favorite erotic podcasts to keep the good times going. Erika Lust Image Credit: SheKnows One site Engle recommends is Erika Lust, which she says makes “queer, female-lens centered movies that are actually really high quality.” This site is all about “cinematic, artsy porn” that has actual narratives (love!) while prioritizing representation and ethical standards. If gorgeously-shot films about sapphic sex parties and swingers’ game nights sounds up your alley, click away. Dipsea Image Credit: SheKnows OK, one more audio erotica, just for fun. Dipsea is yet another excellent example of how sexy and fun it can be to tune in and listen to some sexy voices talking about sexy things. With its clean and beautiful interface, inclusive and diverse casting, and thoughtful, consent-minded stories, you’ll love to plug in and enjoy pretty much everything in their library. PinkLabel.TV Image Credit: SheKnows Another one of Engles’ favorites, PinkLabel.TV offers a true banquet of choices for your viewing pleasure. You can browse through categories like The Feminist Porn Gaze, Art Porn, Queer Porn, and Group Sex — and that’s just a taste. “Get experimental and just browse for a while until you find something that gets you going,” Engle advises. “It can be a really fun learning experience.” Bellesa Image Credit: SheKnows Imagine if Pornhub or RedTube became way, way more unapologetically female-friendly — that, dear friends, is Bellesa. You’re welcome, and enjoy. Sssh.com Image Credit: SheKnows Billed as a “smart and sexy erotic destination for women, by women,” Sssh.com allows you to access a variety of content, from videos to reading materials, all geared toward women. You’re sure to find a medium that gets the job done. XConfessions Image Credit: SheKnows Created by feminist adult filmmaker Erika Lust, XConfessions brings very real, very sexy stories submitted by various folks to life. Yes, it’s as hot as it sounds. Literotica Image Credit: SheKnows If you’re more stimulated by words than images or you’re looking for a quieter, more stealth porn session, head over to Literotica and let your imagination run wild thanks to the enticing stories submitted there. Vivid-Ed Image Credit: SheKnows Part of Vivid Entertainment and run by sex educator and podcaster Tristan Taormino, Vivid-Ed lives up to its name with articles, movies, photos, and more to help you become your best, most empowered sexual being. Kink Image Credit: SheKnows Whether you’re already an experienced lover of kinky sex acts or are just looking to test the
Stopping JAK Inhibitors for Pregnancy: What Happens to Hair in AA? — Donovan Hair Clinic
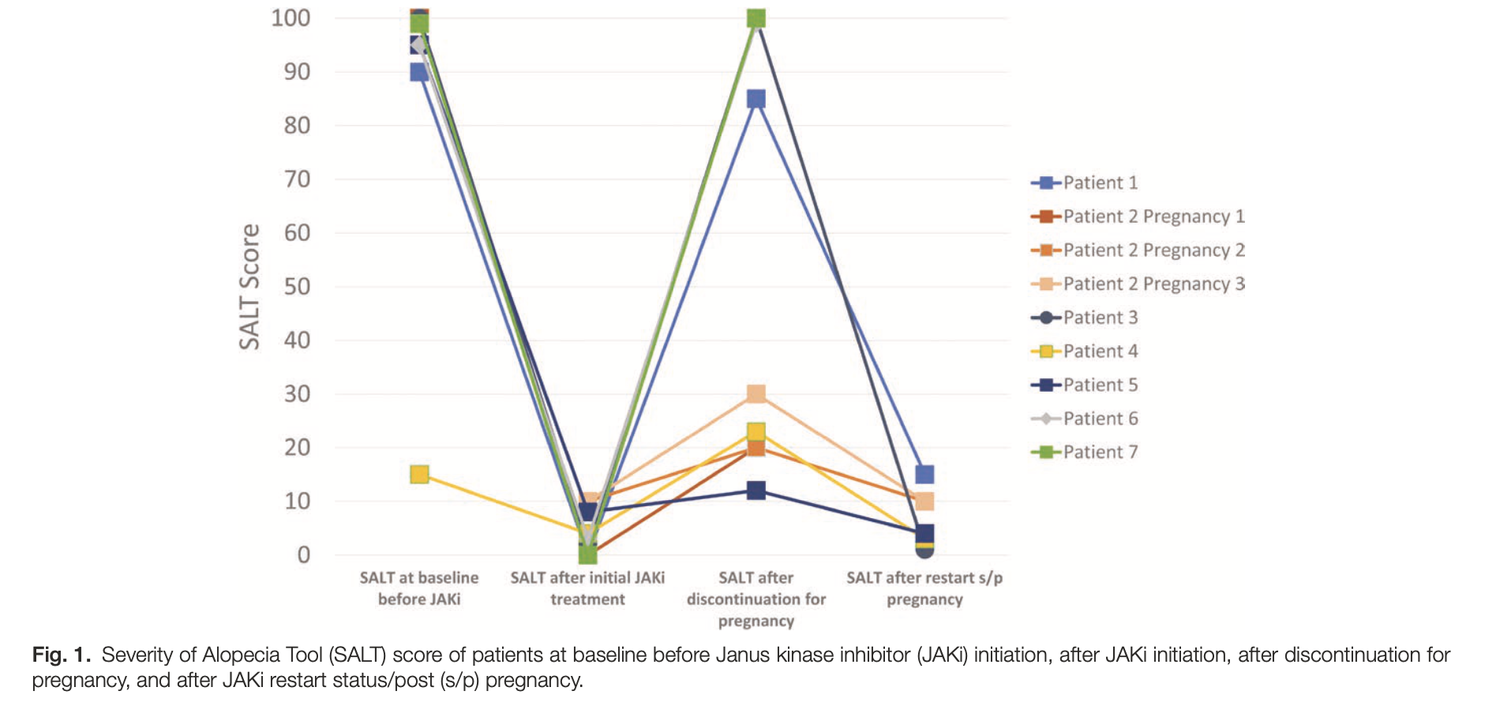
February 15, 2026 BACKGROUND & PURPOSEJanus kinase inhibitors (JAK inhibitors) can help severe alopecia areata (AA) regrow hair. But because safety in pregnancy isn’t fully known, and recommendations are now for women stop treatment when trying to conceive. This often leads to fear of hair loss returning. The purpose of this study was to describe what happens to scalp hair when JAK inhibitors are stopped for pregnancy — and what happens after restarting them postpartum. METHODSDoctors followed 9 women with severe AA through 14 pregnancies. All stopped oral JAK inhibitors before or early in pregnancy. Hair loss severity was measured using the SALT score before treatment, after stopping treatment, and after restarting postpartum. RESULTSEvery woman experienced significant hair loss after stopping treatment. However, once JAK inhibitors were restarted — usually within 4 months after delivery — patients regrew their hair, often back to or better than before. FIGURE 1 FROM Ogbutor C, Chen L-C, Kalil LL, et al. Discontinuation and restart of Janus kinase inhibitors due to pregnancy in alopecia areata: a case series. Int J Womens Dermatol. 2025;11:e218. used with creative commons license. CONCLUSIONSWomen with AA who must stop JAK inhibitors during pregnancy should be counseled that hair shedding is highly likely. The encouraging news is that restarting treatment after delivery (and after breastfeeding is done) led to meaningful regrowth in all cases. This study highlights the emotional burden these women face and the need for clearer pregnancy-related treatment guidelines in AA. REFERENCEOgbutor C, Chen L-C, Kalil LL, et al. Discontinuation and restart of Janus kinase inhibitors due to pregnancy in alopecia areata: a case series. Int J Womens Dermatol. 2025;11:e218. This article was written by Dr. Jeff Donovan, a Canadian and US board certified dermatologist specializing exclusively in hair loss. Source link
Botox for Migraine: What You Need to Know About This Preventive Treatment
This post may contain affiliate links. Migraine Strong, as an Amazon Affiliate, makes a small percentage from qualified sales made through affiliate links at no cost to you. Botox may be best known for smoothing wrinkles, but for many living with chronic migraine, it’s also a powerful tool to help prevent attacks. Approved by the U.S. Food and Drug Administration (FDA) in 2010, Botox for migraine has become a widely used and effective preventive treatment. Whether you’re just beginning your migraine management journey or have tried several preventive medications without success, Botox might be worth considering. In this article, we’ll break down what Botox is, how it works, who it’s for, and what you can expect before, during, and after treatment. ** While Migraine Strong writes about the latest in migraine treatments, this is not medical advice. We are patient educators. All information you read should be discussed with your doctor. What Is Botox? Botox is the brand name for onabotulinumtoxinA, a purified neurotoxin derived from the bacterium Clostridium botulinum. While it’s widely known for cosmetic use—reducing fine lines and wrinkles—it’s also FDA-approved for several medical conditions, including chronic migraine. The discovery that Botox could help with migraine was somewhat accidental. Patients receiving Botox injections for cosmetic reasons reported fewer headaches, prompting researchers to explore its effects on migraine. Clinical trials confirmed its effectiveness in reducing the number of headache and migraine days for people living with chronic migraine. Botox was officially approved for chronic migraine in 2010 by the FDA. How Botox Works for Migraine While the exact mechanism isn’t fully understood, Botox is believed to work by blocking the release of certain neurotransmitters involved in the pain pathways associated with migraine. These neurotransmitters signal pain, and Botox may help interrupt that communication before an attack begins. Unlike acute treatments, which are taken once a migraine attack has started, Botox is a preventive treatment. The goal is to reduce the number, frequency, and severity of migraine attacks over time. On average, Botox reduces 8 to 9 headache and migraine days per month [1]. Who Qualifies for Botox for Migraine? Botox is approved only for chronic migraine, not for episodic migraine. According to the International Classification of Headache Disorders, chronic migraine is defined as: 15 or more headache days per month, and At least 8 of those days must include migraine features, such as head pain, sensitivity to light or sound, nausea, or visual aura Symptoms must persist for more than 3 months In most cases, insurance providers require that patients try and fail two or more preventive treatments—either due to lack of effectiveness or intolerable side effects—before approving Botox. This is called Step Therapy. The Botox Procedure: What to Expect Botox for migraine is typically administered by a neurologist or headache specialist trained in the PREEMPT injection protocol, which involves: 31 small injections Across 7 specific muscle areas in the head, neck, and shoulders Every 12 weeks (approximately every 3 months) Botox for migraines injection sites Botox for migraines injection sites Botox for migraines injection sites Botox for migraines injection sites Botox for migraines injection sites The treatment itself usually takes between 5 to 15 minutes. A fine needle is used to inject small amounts of Botox into the targeted areas. Most patients describe the sensation as a series of small pinches or stings, and the procedure is generally well tolerated. There is no required recovery time—you can typically drive yourself home afterward and return to your regular activities the same day, though some people prefer to rest for a few hours. Most doctors recommend not exercising or lifting for 24 hours after the procedure. The Cleveland Clinic has a good overview of what you should and shouldn’t do after Botox for migraine. When Will You See Results? Botox is not an instant solution. Results typically appear gradually over time. According to studies and patient reports: Some people experience improvement within 4 weeks Most see significant results after 2 to 3 treatment cycles, spaced 12 weeks apart On average, Botox reduces 8 to 9 headache or migraine days per month [1] Research shows that even if a patient doesn’t respond after the first cycle, they may respond after the second or third. A large study found that: ~25% of people who didn’t improve after the first treatment cycle responded after the second Another ~25% who didn’t respond after the second round improved after the third This supports the recommendation to try Botox for at least three full treatment cycles before evaluating its effectiveness [3]. Predicting Whether Botox Will Work for You While there’s no guaranteed way to know whether Botox will work for an individual, some studies have looked for possible predictors. A study by Dr. Rami Burstein suggested that the type of migraine pain a person experiences might help indicate whether they’ll respond to Botox. The research found: People who describe their pain as “imploding” (a crushing or inward sensation) were more likely to respond to Botox People who describe “exploding” pain (as if pressure is building inside the head) were less likely to respond In fact, 92% of non-responders reported “exploding” pain, while 74% of responders described “imploding” or “ocular” migraine pain [5]. Overall, about 65% of chronic migraine patients respond to Botox after three cycles [4]. Botox Side Effects and Safety Botox is considered a safe and generally well-tolerated treatment. However, as with any medical procedure, side effects can occur. The most commonly reported side effects include: Neck pain Headache or worsening of migraine symptoms Eyelid or eyebrow drooping (ptosis) Muscle stiffness or weakness near the injection sites Mild bruising or swelling [6], [7] The good news is that side effects tend to decrease with each subsequent treatment [8]. If side effects persist, your doctor may adjust the dose, recommend a different botulinum toxin like Myobloc, or consider discontinuing the treatment altogether. The first time I tried Botox, I felt like my attack frequency increased, and I ended up giving up on it too soon. I
#FGblog – Amoebiasis? If you en-cyst…
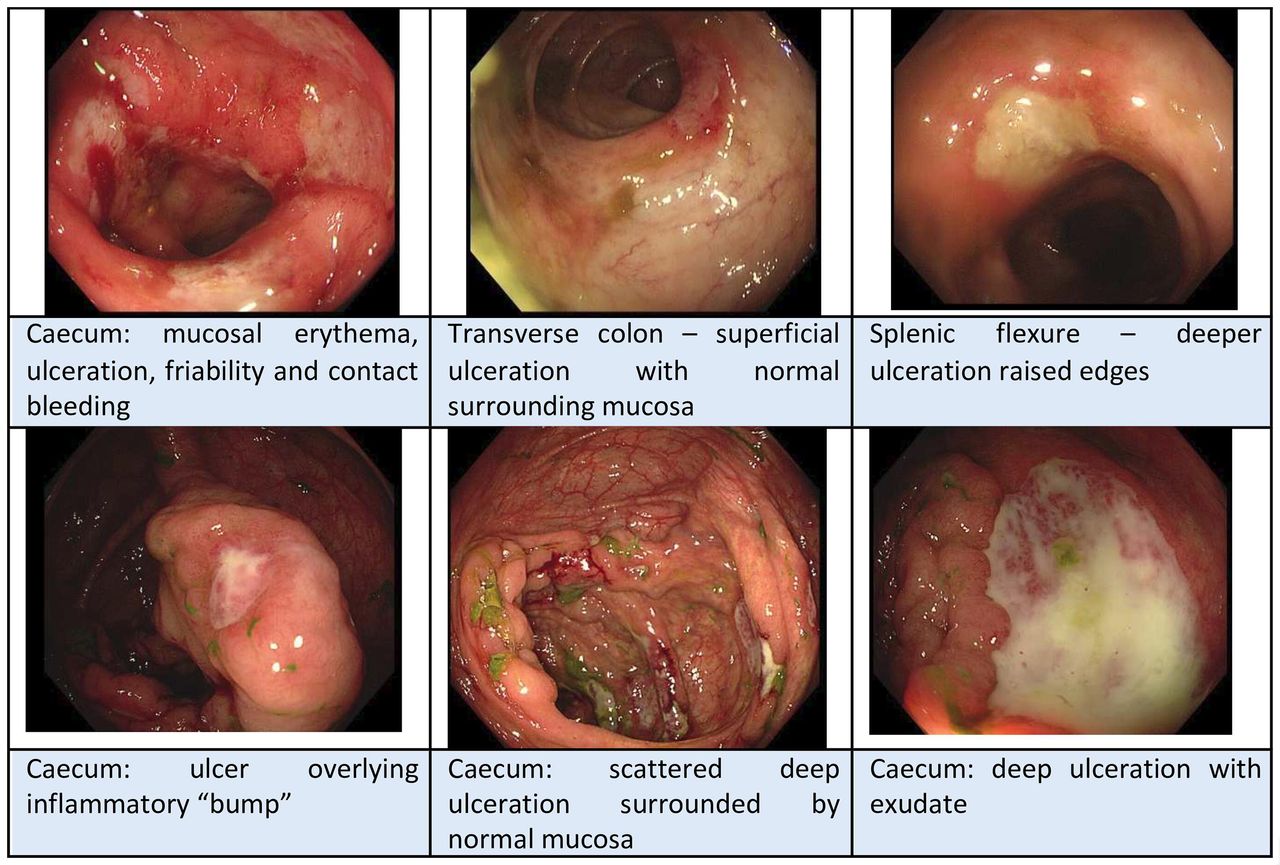
In this blog the FG team would like to highlight our latest Open Access review on “Recent advances in the diagnosis and management of amoebiasis” by Cooney et al. This comprehensive but highly readable article will take you from wherever you are on the ‘zero to hero’ spectrum of amoebiasis to an overnight expert. FG is no stranger to amoebiasis, covering management of liver abscess and a case report of amoebic colitis over the years, but this review is timely given the increasing recognition of amoebiasis as a global health problem and a rise in imported cases to the UK. The article kicks off by covering the pathophysiological and epidemiological background to Entamoeba histolytica infection, including a helpful diagram of the life cycle of E. histolytica, highlighting its infective stage and the points at which it causes disease. The encysted trophozoites are hardy, surviving for up to 90 days following excretion. Amoebiasis is sadly still responsible for 55,000 deaths a year, especially in children under 5 and in lower income countries, although morbidity is declining owing to improved sanitation and management of symptomatic infection. Interestingly the reverse trend is being seen in high income countries, with an increased loss of disability-adjusted life years, most likely due to increased travel and migration. That said, acquiring the infection in non-endemic countries is well recognised and so a travel history should not be a pre-requisite to considering the diagnosis. Immunosuppression as a risk factor for developing amoebic colitis, and for increased severity of disease is hugely important for frontline gastroenterologists to be aware of. Amoebic colitis is an IBD mimic, and the perils of immunosuppressing patients with E. histolytica infection are clear, whether with corticosteroids, immunomodulators or advanced therapies. E.histolytica laboratory testing is often not part of a routine pre-immunosuppressant screen in the UK (it does not feature in the BSG guidelines), although the authors are clear that it should be. In endemic settings, the need to ‘look before you leap’ with immunosuppression is critical to avoid potentially life-threatening consequences. The high rate of toxic megacolon and perforation (and a 40% mortality rate) with fulminant amoebic colitis is of concern, with certain groups being at higher risk. The section on amoebic liver abscess (ALA) as the most common extra-intestinal manifestation of amoebiasis is welcome. Interestingly, most patients with amoebic liver abscess do not have amoebic colitis simultaneously. The authors carefully lay out the different diagnostic approaches, with their relative merits and drawbacks. Whereas expensive molecular techniques (e.g. PCR) may be commonplace in higher income settings, light microscopy or point-of-care antigen detection may be more appropriate in resource-limited healthcare environments. Colonoscopy, although not needed to seal the diagnosis in most cases, will inevitably be part of the diagnostic work-up, and we found the images of the pathognomonic ‘bump’ sign and other endoscopic features very helpful. Treatment of all cases, symptomatic or not, is crucial. Dual treatment with a ‘tissue amoebicide’ (e.g. metronidazole) and a ‘luminal amoebicide’ (e.g. paramomycin) prevents recurrence. Duration of treatment depends on whether it is amoebic colitis or ALA being treated. Also, do not forget the simple but crucial measures of universal enteric precautions, and contact tracing with a test and treat approach. Far from being a niche health problem confined to medical school finals and membership exam trivia, the ins and outs of amoebiasis are a must-know for gastroenterologists, and we hope you will go straight from this blog to read this engaging article. References Cooney J, Siakavellas SI, Chiodini PL, et al Recent advances in the diagnosis and management of amoebiasis. Frontline Gastroenterology. Published Online First: 07 October 2024. doi: 10.1136/flgastro-2023-102554 Trillos-Almanza MC, Restrepo Gutierrez JC How to manage: liver abscess Frontline Gastroenterology 2021;12:225-231. Meade S, Arora A, Goderya R, et al Unusual case of severe colitis Frontline Gastroenterology 2019;10:322-324. The post #FGblog – Amoebiasis? If you en-cyst… appeared first on Frontline Gastroenterology Blog. Source link

Preparing for a New Doctor When You Live With Chronic Pain
Many of us living with pain have experienced the challenge of no longer being able to see our familiar doctors. In my state of Rhode Island, along with those who are naturally retiring, many have also chosen to leave to receive the more reasonable pay that they deserve in a different state. Whatever the reason, this leaves us searching for a new doctor. However, for those of us living with a chronic condition, this process can be extremely challenging. Our mission is to find a new doctor who is willing to take us on despite our complications. Chronic pain sure puts a monkey wrench into the journey of searching. I live with Ehlers-Danlos syndrome, which is an incurable, painful, and complicated condition. Therefore, finding a doctor who is willing to add me to their practice is not so simple. When searching for a new physician, we must share the truth about our difficult journey, while also showing them that we are taking an active role in working to help ourselves. I have found that since it is hard to find an EDS-knowledgeable doctor, I instead search for one who is willing to listen to me, believe in me, and trust me—one who is willing to learn with me, to search for ways to improve the quality of my life with my condition. Framing my search in this way helps me find a match that is supportive and fulfilling for me. While it can be difficult to establish a doctor-patient relationship when you have chronic pain, your journey may help pave the way for the next patient who is also struggling with your condition. So what should you be prepared to share with a new doctor? I’ve found it helpful to bring the following: Medication list, including the dosage and date each was started Medication reaction list Any diagnoses you have been given, and the dates of diagnosis Dates and details of any body scans or imaging you’ve had done Dates and details of any surgeries or procedures you’ve had, and where they took place Insurance cards Name and contact information of the pharmacy you use List of doctors who are presently working with you I am sure you have times of frustration living with your condition. And, as in my case, it’s possible a doctor won’t be able to cure you. But I have found that developing a kind and caring relationship with my doctors has made my visits pleasant, and the compassion they have shown me makes a difference in my care. Listening, believing, and caring for me means the world, and I have worked with each provider to create this type of relationship. When you have found a good match with a provider who is willing to add you to their practice, consider, during your appointment, asking your doctor how they are doing. They tend to be initially shocked, but it brings on appreciation and a chance to get to know each other in a caring way that will help to nurture your relationship and mutual respect. May life be kind to you… —by Ellen Lenox Smith Source link

Causes of Premature Menopause and Early Menopause
What is menopause? Menopause occurs when you’ve gone 12 months without a period. Most women experience menopause between the ages of 45 and 58. The average age of menopause in the U.S. is 51 Natural menopause The decline in female hormones that happens naturally with age. Induced menopause When medical treatments like cancer treatments or surgery temporarily or permanently shut down the ovaries so they no longer make estrogen and progesterone. Induced menopause happens quickly — within a few weeks or even overnight — and can cause early or premature menopause. Premature menopause = Menopause before age 40 Early menopause = Menopause before age 45 Factors that cause or are associated with premature or early menopause Risks of early or premature menopause Living longer without the health benefits of higher estrogen levels may increase your risk for health problems like: Talk to your healthcare provider about your risk If you think you may be at risk for early or premature menopause, talk to your healthcare provider. Together you can figure out a plan. This educational resource was created with support from Bayer, a HealthyWomen Corporate Advisory Council member. Source link

How To Do a Breast Self-Exam & Distinguish Lumps
A breast self-exam is when you check your breasts, by sight and by touch, for any changes, like a new lump. And many professionals will agree that becoming familiar with what your breasts normally look and feel like is a great way in which to become aware of any changes for early concerns or cancer detection. Today, we’re going to be looking at breast lumps, what it feels like, the different types, and how to check for breast lumps aka do a breast self-exam. What Is a Breast Lump? A breast lump is a localised swelling, bump, or mass in the breast that feels different from the surrounding breast tissue, and it can vary in size, texture, and tenderness. And while it can be completely daunting, it’s important to remember that the majority of breast lumps are not breast cancer. In fact, there are many conditions that may cause benign (non-cancerous) breast lumps. On the other hand, the absence of a noticeable breast lump doesn’t mean that breast cancer cannot or hasn’t developed. This is why it’s important for women to do self-exams monthly from the age of 18, and for women over the age of 40 to go for an annual mammogram. What Does a Breast Lump Feel Like? A breast lump can feel different depending on its cause. It can be found in or around the breast tissue, or in the underarm area, and its size can vary from a pea to larger than a golf ball. Some common sensations and textures include: Firm or Hard This may feel like a solid mass within the breast Cancerous lumps are often hard and irregular Benign lumps can also feel firm Smooth and Moveable Often round or oval Can move slightly under your fingers Is often common with fibroadenomas (non-cancerous growths) Soft or Fluid-Filled May feel squishy or like a small water balloon Often tender before a menstrual period Common with breast cysts Tender or Painful Fixed in Place A lump that doesn’t move easily The Different Types of Breast Lumps For clarity, we’ll divide this up into two sections; benign and malignant. Benign means non-cancerous, and malignant means cancerous. Benign Breast Lumps Fibroadenoma: occurs primarily in women in their 20s and 30s, the lump may feel rubbery and move around freely, it’s often painless, varying in size, and can form anywhere in the breast tissue. Fibrocystic breasts: may come about in women with dense breasts, occurs naturally due to hormonal fluctuations during menstruation, may feel lumpy, swollen, and sore before a period. Breast cyst: a fluid-filled sac inside the breast that’s round or oval and may feel soft or firm. They’re smooth, moveable, can be tender, and may change in size during menstruation. Fat necrosis: scar tissue from injured breast fat that may occur after trauma, surgery, or radiation. They’re a firm, round lump, sometimes causing skim dimpling, and may mimic cancer on imaging. Lipoma: a slow-growing, fatty lump mass made of fat cells that are soft, painless, and move easily under the skin. Breast abscess: an infection (pocket of pus due to a bacterial infection) that causes a painful lump, and is often associated with breastfeeding. Symptoms include redness, swelling, and a fever. Intraductal papilloma: a small wart-like growth inside a breast, near the nipple, that can lead to nipple discharge. Malignant Breast Lumps Cancerous breast lumps are caused by abnormal, uncontrolled cell growth in breast tissue. Unlike benign lumps, they can invade surrounding tissue and spread (metastasise) to other parts of the body. Invasive ductal carcinoma (IDC): the most common type of breast cancer that begins in the milk ducts and spreads into surrounding breast tissue. Symptoms may include a hard, irregular lump, skin dimpling, and nipple inversion. Invasive lobular carcinoma (ILC): the second most common type of breast cancer that starts in the milk-producing lobules and spreads into nearby tissue. Symptoms may include thickening instead of a distinct lump, fullness or swelling, and subtle breast shape changes. Ductal Carcinoma in situ (DCIS): stage 0 breast cancer that’s abnormal cells confined to the milk ducts that haven’t invaded the surrounding tissue. Symptoms may include nipple discharge, but there is often no lump. Inflammatory breast cancer: a rare but aggressive form of breast cancer of which the cancer cells block the lymph vessels in the skin of the breast. Symptoms may include a red, swollen breast, warmth, skin that looks like an orange peel, and often without the presence of a distinct lump. Triple-negative breast cancer: hormone receptor-negative cancer, which is when there is a lack of estrogen receptors, progesterone receptors, and HER2 protein. HER2-positive breast cancer: when there are high HER2 protein levels, promoting rapid growth. Paget disease of the breast: a rare form of breast cancer affecting the nipple and often the areola. Symptoms may include red, flaky nipple skin, burning or itching, and a possible underlying lump. How To Check for Breast Lumps At-Home A simple, step-by-step guide on how to do a breast self-exam (BSE)… 1. Get in Front of a Mirror Stand undressed from the waist up in front of a mirror with your arms relaxed. Take a look at your breasts for changes in size or shape, swelling, skin dimpling (like an orange peel), redness or a rash, nipple inversion, or unusual discharge. Then, raise your arms overhead and repeat. After, place your hands on your hips pressing firmly and repeat again. 2. Lie Down Lie down and place a pillow under your right shoulder. Put your right arm behind your head. Use the pads of your three middle fingers on your left hand and choose one pattern: Circular: small circles from outer breast towards the nipple Vertical lines: up and down strips Wedge pattern: from outer breast toward the nipple and back out Use three types of pressure: light for just beneath the skin, medium for the middle tissue, and firm for the deep tissue near the ribs. Cover the entire breast, armpit area, area to the collarbone, and down
The Gut Microbiome in Alopecia Areata: Is it Really a Mainline Therapy? — Donovan Hair Clinic
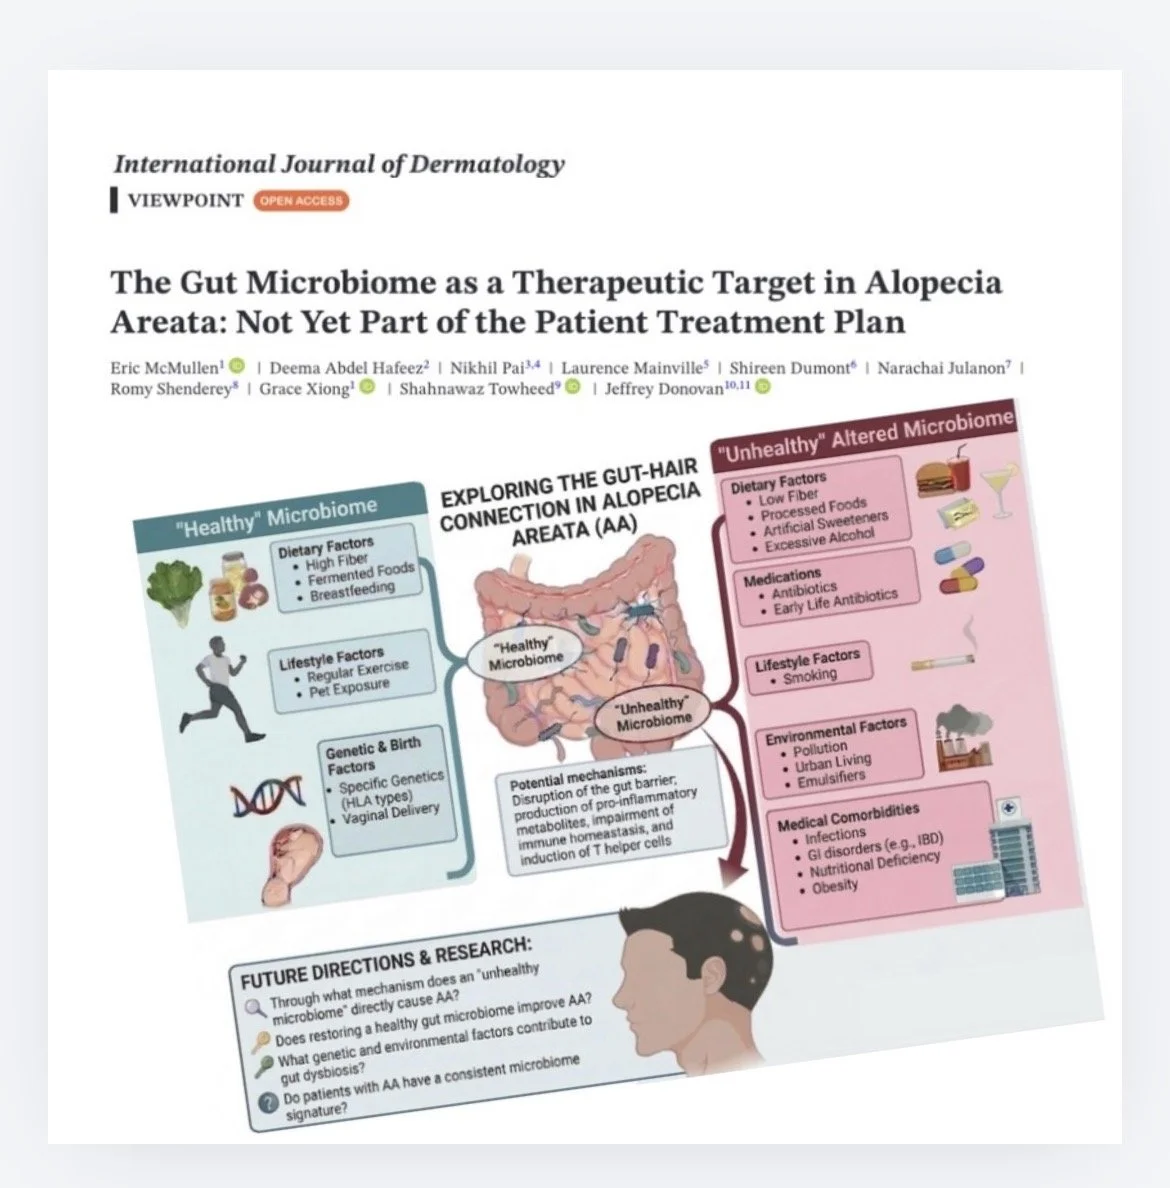
Our Microbiome Paper is Now Published It’s a great joy to share our new paper exploring the gut microbiome and whether it should currently be considered part of an evidence-based treatment plan for patients with alopecia areata. The paper is available Open Access in the International Journal of Dermatology. There has been growing interest in the “gut–skin axis” and whether gut dysbiosis may contribute to alopecia areata by influencing immune regulation, inflammation, and T-regulatory cell function. Patients are increasingly asking about probiotics, gut microbiome testing, dietary changes, and even fecal microbiota transplantation (FMT) as possible treatment strategies. Is it worth adding these evaluations and treatments? In this paper, we examined the available evidence surrounding microbiome-directed therapies in alopecia areata. While some small studies have identified potential bacterial biomarkers and very isolated reports have described hair regrowth following FMT, the overall evidence remains limited and inconsistent. A recent randomized trial of probiotics didn’t show a significant benefit. We are grateful to Wiley and the International Journal of Dermatology for publishing this Viewpoint paper. At present, the science is simply not strong enough to support routine microbiome testing or microbiome-targeted therapies as standard care for alopecia areata. Probiotics, dietary interventions, and FMT remain interesting areas of investigation—but not yet part of the evidence-based treatment plan. More rigorous longitudinal studies and stronger clinical trials are needed before these approaches can move from exciting theory to everyday clinical practice. Someday, we’ll better understand the link – and be able to better target therapies! I’ve enjoyed working with our group on this subject. Congratulations to first author Dr Eric McMullen from the University of Toronto for leading the way and for all our great discussions on this topic. And thanks to all our colleagues for their wonderful insights and hard work! Reference McMullen E, Abdel Hafeez D, Pai N, et al. The gut microbiome as a therapeutic target in alopecia areata: not yet part of the patient treatment plan. Int J Dermatol. Source link

Makary out as FDA commissioner
Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Key takeaways: Martin Makary, MD, MPH, has reportedly resigned. Inconsistency was a major component of his tenure, an expert said. Martin Makary, MD, MPH, is resigning as FDA commissioner. Politico was first to report the news on Tuesday, citing an administration official who was granted anonymity. The official told Politico that HHS Secretary Robert F. Kennedy Jr. made a decision months ago to “move on from Makary,” but the president also had to sign off. Kyle Diamantas, JD, will now lead the FDA as an acting commissioner, according to Politico. Diamantas is currently the FDA’s deputy commissioner for human foods. The FDA has not yet responded to Healio’s request to confirm the reports. Arthur L. Caplan, PhD, a professor and founding head of the division of medical ethics at NYU Grossman School of Medicine, told Healio that “it’s clear there’s a lot of dissatisfaction with [Makary], and has been for some time.” “I think the main reason for that is he’s been inconsistent at times, trying to approve drugs or speed up pathways — at other times, hindering drugs or treatments for approval,” he said. “Patient groups don’t understand what the hang up is. They’ve been pushing hard against that. One thing the FDA needs is consistency. Manufacturers want it; they need to know where the goal posts are to enable them to get across the approval line. Patients want more and more to be allowed to take risks with things that look promising. He was very inconsistent in response to that wish.” The other issue, Caplan said, is that “other things have slowed down because of cuts in personnel. That makes the biotech and pharmaceutical industries very anxious. I think Trump himself has been for some time on the side of hurrying up drug approval processes. I’m expecting that’s what we’re going to see in the next nominee to be the commissioner: speed over, if you will, caution.” Editor’s Note: This is a developing story. Please check back soon for more details. For more information: Arthur L. Caplan, PhD, can be reached at primarycare@healio.com. Sources/Disclosures Source: Healio Interviews Reference: Disclosures: Caplan reports no relevant financial disclosures. Ask a clinical question and tap into Healio AI’s knowledge base. PubMed, enrolling/recruiting trials, guidelines Clinical Guidance, Healio CME, FDA news Healio’s exclusive daily news coverage of clinical data Learn more Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Source link

The Migraine Trust urges government to incorporate migraine into the renewed Women’s Health Strategy
Migraine is a significant health issue that disproportionately affects women. Around 10 million people in the UK live with migraine and women are two to three times more likely to experience migraine than men. Migraine in women often worsens around menstruation, and has strong links to contraceptive choices, pregnancy, post-partum, and menopause. It is therefore no surprise that the lifetime prevalence of migraine is reported as 33% in women and 13% in men – before puberty, migraine frequency is the same in both sexes. Despite its prevalence and debilitating impact, it was absent from the renewed Women’s Health Strategy published earlier this week. While we welcome the government’s revival of a dedicated plan to tackle gender inequity in the health system, this is a significant missed opportunity. It is especially disappointing given that migraine sits squarely within the strategy’s four priorities. First, migraine is a condition that affects women disproportionately and often differently across the female life course. Second, it is a clear example of women’s pain being minimised or dismissed, with many women reporting that their migraine is not taken seriously, dismissed as “just hormones” or “everyday stress.” Third, it is highly suited to the strategy’s proposed shift toward earlier intervention and stronger community-based pathways – better diagnosis and treatment in primary care would prevent the condition worsening and the need for repeated appointments within secondary care. Finally, migraine has a substantial impact on work, caring responsibilities, and quality of life, making it highly relevant to the strategy’s wider goals on participation, productivity and reducing the toll of long-term conditions. Treating migraine as a priority implementation case would be a practical and credible way for government and the NHS to show that the strategy will deliver for women with common, painful, disabling but often overlooked conditions. The Migraine Trust therefore urges the government to act now to improve the migraine experience for millions of women by applying the strategy’s existing commitments to migraine care. The government can do this through: 1. Formal recognition Government and NHS England should explicitly recognise migraine as a condition that falls within the strategy’s commitment to improve care for conditions that affect women disproportionately or differently. 2. Better community pathways Integrated Care Boards should be tasked to improve migraine pathways in primary and community care, with particular attention to menstrual migraine, medication overuse, prevention, and links to reproductive health. 3. Taking women’s migraine pain seriously Implementation of the strategy’s commitments on listening to women and acting on repeated presentation should include migraine, so that women do not have to fight for a proper diagnosis or an effective care plan or review. 4. Stronger data and accountability Migraine should be included in relevant women’s health improvement metrics, including patient experience, access to appropriate treatment, and avoidable urgent or emergency care use. 5. Research across the female life course Research and innovation priorities should reflect the role of sex differences and hormones in migraine, including menstruation, pregnancy, post-partum change, and menopause. The Women’s Health Strategy was designed to improve the lives of women with common, disabling conditions that have too often been neglected. To succeed in this aim, migraine must be included in the strategy’s implementation phase. Source link


