

Weight-loss drugs like GLP-1’s have boomed in popularity over the last few years, despite the very real side effects, which range from hair to severe gastrointestinal distress. Now, a new class of medications —amylin-based weighty loss drugs — are showcasing a different path forward. A new international study found that people taking one such drug, petrelintide, lost weight while avoiding the type of digestive side effects (like nausea, vomiting, constipation and diarrhea) that can often derail treatment for those using GLP-1s. For those of us who are interested in the benefits of a weight-loss drug but not so jazzed about the GI distress that comes with options like Ozempic, Wegovy, or Mounjaro, it’s welcome news — but the study found that amylin-based drugs may not be quite equal when it comes to the amount of weight coming off. Related story John Goodman Opens Up About Weighing Nearly 400 Pounds and the ‘Vicious Cycle’ of Drinking What are amylin-based obesity drugs, and what is petrelintide? Amylin-based obesity drugs use an analogue of a hormone, amylin, released by the pancreas alongside insulin, per Yale Medicine. Amylin regulates your blood sugar and gives you a feeling of fullness by slowing down the rate at which food leaves your stomach, which helps to suppress your appetite. The effects are similar to a GLP-1 medication, but they work via different mechanisms: amylin-based drugs use an analogue of the pancreatic hormone amylin, while GLP-1s mimic or amplify the effect of glucagon-like peptide-1, which is released by your liver. Petrelintide is a once-weekly injectable amylin analogue drug highlighted in the new study, a medication developed by Zealand Pharma in partnership with Roche. While reporting around the study highlighted how its side effects and weight loss matched up against GLP-1 drugs, the drugs haven’t been compared in a head-to-head trial. Still, we’re able to draw a few tentative conclusions from the research. What did the study find? The recent study on petrelintide, ZUPREME-1, was released in September as a randomized, double-blind, placebo-controlled Phase 2 dose-finding trial (funded by Zealand Pharma, the makers of petrelintide). It was conducted at 32 sites internationally, including public hospitals and private clinics in countries like the US, Poland, and Romania, and included 485 participants with obesity, with a mean BMI of 36.7 to 37 kg/m2, and a mean body weight of about 107 kg (235 pounds). The participants’ mean age was 48. The study found that after 42 weeks on petrelintide, participants had lost about 10% of their starting weight, on average, compared to just 1.7% for those participants on the placebo. Specifically, participants on the smaller, one-milligram dose lost 8.7% of their bodyweight, versus 10.5-10.7% on the seven-milligram dose. All participants (including those on the placebo) also received counseling on weight loss through diet and at least 150 minutes of exercise per week. The weight loss is lower than what patients on GLP-1’s typically lose. Per Drugs.com, people on semaglutide (like Ozempic and Wegovy) often lose, on average, 15-19% of their bodyweight; for people on tirzepatide (like Zepbound), it’s around 20-21%. But notably, the study participants on pertrelintide lost this weight without experiencing some of the grueling side effects that often come with GLP-1s. The less significant weight loss might be the tradeoff for lighter side effects. So what were the side effects of petrelintide? The study found that petrelintide’s most common side effect was nausea, which was experience by 20% of participants on the drug (versus 6% on the placebo). Other side effects included vomiting (3% of petrelintide users) and diarrhea (7% of petrilintide users). But the researchers also found that at the maximally effective dose of pertrelintide (that seven-milligram mark), there was no vomiting reported at all — and none of the participants had to discontinue treatment due to GI side effects. “Rates of nausea with petrelintide are less than half of those observed with GLP-1 medications,” noted lead researcher Timothy Garvey, MD, of the University of Alabama at Birmingham, in an interview with HCPLive. “Rates of constipation, diarrhea, and vomiting roughly approximated those observed in placebo,” he continued. “This is a well-tolerated medication.” The side effect conversation is an important one. The gastrointestinal side effects caused by GLP-1’s lead to 41% of users to suffer in silence, self-adjust the medications, or even stop taking them altogether, according to a national survey from Oshi Health. What happens next? Petrelintide isn’t yet approved by the FDA, so it’s not available yet in the US, and these results still need to be reproduced in further trials. But the news is looking positive: in phase 2b trial results released earlier this month, 220 people with overweight or obesity and type 2 diabetes reported losing up to 9.5% of their bodyweight over 28 weeks, compared to 2% with placebo. The next step is to test the drug again in a Phase 3 trial. It’s also worth noting again that we don’t know how petrelintide performs in a head-to-head trial versus a GLP-1 drug — we can only compare studies of both drugs done separately. Still, if a weight-loss drug with potentially less intense side effects than a GLP-1 is piquing your interest, it’s worth keeping an eye on petrelintide and talking to your doctor if it does become available. Source link
The World’s First Spinal Cord Transplant has been Performed
Dr. Xiaoping Ren (China) and Russian surgeons performed the world’s first spinal cord transplant in October 2026. On extremely rare occasions, I cover developments from the medical world that are unrelated to hair. Initially, I planned to ignore yesterday’s news about the world’s first spinal cord transplant having been performed in Russia. But then I read that the lead surgeon involved is the renowned Dr. Xiaoping Ren from China, so I had to write this post. Long-time readers might remember when I covered Dr. Ren and Dr. Sergio Conavaro several times between 2015 and 2017. At the time, they attained global infamy due to their plans to perform the world first head transplant. Or more accurately, a full body transplant onto an existing head. They even got over 100 volunteers who wanted to get the procedure, and were set to perform it on Russian Valery Spiridonov. But, perhaps thankfully, this never materialized. Side Note: I am very curious to know the current situation of the world’s first ever skull and scalp transplant recipient James Boysen. The Texan underwent the procedure in 2015 and seemed very satisfied with the outcome a year later. Including bonus brand new scalp hair. I contacted him on Linkedin a while back, but received no response. The World’s First Spinal Cord Transplant Performed in Russia The world’s first spinal cord transplant was performed last week in Russia, and even the mayor of Moscow announced this on his Max channel. The pioneering 12-hour surgery was performed at the Sklifosovsky Research Institute of Emergency Care. The patient, who was facing complete immobility, now has a chance to recover. However, some scientists have voiced skepticism. Per “New Scientist“, the procedure: “Involved removing a damaged segment of a person’s spinal cord, three years after the injury, and replacing it with a section from a brain-dead donor.” According to Dr. Ren (who currently conducts his surgeries at China’s Second Affiliated Hospital of Guangxi University of Chinese Medicine): “Surgeons removed damaged tissue and used microsurgery and polyethylene glycol (PEG), a substance capable of helping cell membranes fuse, to join the donor segment to the recipient’s spinal cord. We have informed the patient of every potential risk and surgical outcome, and the patient’s current condition is good.” Interestingly, in February 2026, Dr. Ren and another team of Russian surgeons performed Russia’s first bilateral hand allotransplant surgery. That complex operation lasted for 13 hours and involved precise reconnection of blood vessels, bones, nerves and tendons. Wouldn’t it be great if Chinese and Russian scientists collaborated on finding a hair loss cure? While China has in recent years finally started to make its mark in treating hair loss, Russia still seems largely absent. See my global list of major hair loss research centers and companies. Below is a YouTube short on the world’s first spinal cord transplant procedure that was done in Russia in October 2026. Source link

Practice good ergonomics early in career to avoid injuries
October 19, 2026 10 min read Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Key takeaways: Musculoskeletal pain and injuries are common among ophthalmologists. Office layout, exercise and equipment all can improve physician ergonomics. Click here to read the At Issue to this Healio Exclusive, “Practice good ergonomics early in career to avoid work-related injuries.” For ophthalmologists, occupational pain can start early. Image: Courtesy of Sunir J. Garg, MD, FACS, FASRS For Cynthia Matossian, MD, FACS, discomfort arose fewer than 5 years into her career. She said surgeons often find themselves in similar positions over the course of their routine work, and repeated motions can wear people down. “There were two areas that I noticed were bothering me after being hunched over the slit lamp day in, day out, week in, week out, and after being in the OR for long days of surgery,” she said. “Those two areas were my neck and upper back area around my shoulder blades.” The discomfort got so bad that she knew if she did not address it, it could have a significant impact on her career. “I told myself, ‘I can’t go on like this,’” she said. “I need to help my body so that I can be an effective and healthy ophthalmologist for as long as possible.” Musculoskeletal pain and injuries are common among ophthalmologists. A 2025 literature review that included data from more than 3,200 ophthalmologists found that the average prevalence of work-related musculoskeletal disorders was about 63%, with neck, lower back and shoulder disorders most affected. The authors also found that more than 7% of ophthalmologists require spine surgery because of cervical spine disease related to disc herniation. Additionally, these disorders push about 13% of ophthalmologists to early retirement, according to the study. Cynthia Matossian When Matossian looked for solutions for her discomfort about 30 years ago, there was not much to work with because not many people talked about the problem, she said. “I started to do some research about it, and ergonomics was not a common topic back in the day,” she said. “It wasn’t discussed, it wasn’t talked about, and you just slouched over and did what you had to do to examine patients. Nobody paid attention to this area.” Deepinder K. Dhaliwal, MD, LAc, said ergonomic problems trace back to the physician’s mindset to put the patient and their comfort first. “We tell ourselves that the patient has to be comfortable, and we’ll withstand an uncomfortable position,” she said. “The problem is that because we do so many exams and so many surgeries in a career, all that poor posture and habits come back to haunt us.” Matossian agreed, saying physicians are taught to push through tough times, exhaustion and pain. “You’re sleepless, but you get through the night,” she said. “We just try to tough it out and power through whatever aches and pains we may be having. These are signs of your body telling you that it is not happy, and perhaps there are simple adjustments that can be made to alleviate those issues completely if you pay attention to them.” The early career experience of Eric D. Rosenberg, DO, was no different. When he started his internship, his first goals were not to hurt anyone else and to help patients. “From day 1 coming out the gate, we’re always inclined to take care of the person in front of us, never ourselves,” he said. “We frequently do it at the cost of ourselves. We don’t care about ourselves because we’ve been trained not to care about ourselves. All aspects of our lives have been trained and geared toward making sure that the people around us are better off than we are.” Common Mistakes When Dhaliwal works with young physicians, there are a few ergonomic issues that she spots right away, including their posture at the slit lamp, which was an issue early in her career. “I used to crane my neck forward, and it’s such a common thing that I see people do because they try to reach the patient,” she said. “The critical thing I do now is lift the patient’s chair up and slide my stool under the footrest so I can get close. I have the patient move to the edge of their seat so that they are leaning forward into the slit lamp, and I can keep my spine and neck straight. That has changed my life.” Dhaliwal said her goal is to keep her ears over her shoulders and ensure she is properly supporting her head when she is examining patients. “The typical head weighs 10 to 12 pounds, but if we flex forward 30°, which is not a lot, that effective weight on our cervical spine is 40 pounds” she said. “You can understand why even when you’re looking down at your phone for a long time, your neck can start to feel uncomfortable.” Sunir J. Garg, MD, FACS, FASRS, said a lot of ergonomic mistakes are caused by environmental factors, including a poor office setup. “Our profession, including our equipment, is set up for everything besides our ergonomic benefit,” he said. “If you walk into one of my exam rooms, I have the computer parallel to the wall on one side, and I have the patient chair at 90° in front of me; that setup is ergonomically not good. I’m trying to type while I rotate and turn my head toward the patient, which causes unnecessary stress on our neck and our back. That twisting motion is bad for a person’s spine.” Garg said common slit lamp setups are wrong

Jon Bon Jovi Recalls 4-Year Recovery After Vocal Surgery
Jon Bon Jovi couldn’t even sing “Happy Birthday.” For a singer who’s spent decades leading stadiums through “Livin’ on a Prayer,” that’s a hard thing to imagine. But in a recent interview with Australia’s A Current Affair, the 64-year-old described just how difficult it was to rebuild his voice after undergoing vocal cord medialization surgery in 2022. “I didn’t lose faith, but had [my doctor] told me it was going to be four years, I might’ve contemplated saying, ‘It’s been great,’” he said. “Because the process was so damn long and I would see the progress, but it was incremental. It was inches. I couldn’t sing ‘Happy Birthday.’” Related story Octavia Spencer Found Out She Had Type 2 Diabetes at a Routine Physical in Her 30s, and Here’s What She Changed Why Bon Jovi Kept Saying No to Touring Bon Jovi said he repeatedly turned down plans to get back on the road because his voice wasn’t where he wanted it to be, even when others thought he sounded fine. “I’ve gone through hell and I would not, could not, compromise the legacy,” he said. “I could not, would not go out and hold the mic out to the crowd.” He was also honest about how stressful performing had become before surgery. “In 2019 and 2022 for sure, every note I was white-knuckling that microphone,” he recalled. “‘Is that in tune? Is that in tune? Is that good enough?’” He added, “That was real. Every night. It was not worth doing.” His wife, Dorothea, didn’t sugarcoat his performance either. After one Nashville performance, he remembered telling her, “That was pretty good!” Her answer? “No. It wasn’t.” Bon Jovi said he appreciated her honesty. ‘I Can Actually Sing Without Thinking About Singing’ Bon Jovi describes his voice as “phenomenal” and being back onstage as “joyous.” But the biggest difference may be how little he has to think about it. “I can actually sing without thinking about singing,” he said. After years of questioning every note, that’s a meaningful change. “The beautiful thing that I aspired to for these years was, I have 18 albums. I want to be able to pick any song from any record and know that I can do them,” he explained. By the end of the band’s Wembley shows, he said, that was happening. His bandmates stayed with him through the uncertainty. In June, Bon Jovi told People that they never doubted him or decided to move on. “The sacrifices that each one of them have made to be there for me is on a whole ’nother level,” he said. “They said, ‘No, we’re with you.’” And after years of second-guessing his voice, he’s giving himself a break from judging every performance. “I haven’t read a single review,” he told A Current Affair. “I didn’t listen to a note and I just say, ‘I was there. I know. I had a great time. I’m having fun again.’” Source link

The FDA has expanded its approval of Skyrizi to include subcutaneous induction for adults with moderately to severely active Crohn’s disease.
October 23, 2026 2 min read Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Key takeaways: The FDA approved a subcutaneous induction regimen of risankizumab for adults with moderate to severe Crohn’s disease. Patients can now start induction therapy at home. The FDA has expanded its approval of Skyrizi to include subcutaneous induction for adults with moderately to severely active Crohn’s disease. Risankizumab (Skyrizi, AbbVie) was approved in 2022 for this patient population as an IV induction regimen followed by subcutaneous maintenance. The FDA has expanded its approval of Skyrizi to include subcutaneous induction for adults with moderately to severely active Crohn’s disease. The latest approval allows patients to start treatment from home with an on-body injector induction pack, according to a manufacturer release. Data from the phase 3 AFFIRM trial supported the approval, the release noted. Results showed nearly twice as many patients who received the subcutaneous induction regimen achieved clinical remission at week 12 when compared with placebo. “One of the things that we as gastroenterologists want to do is use the safest, most effective therapy to hopefully treat [inflammatory bowel disease] early, achieve mucosal healing and prevent need for surgery or other complications in our patients,” Millie D. Long, MD, MPH, FACG, professor of medicine at University of North Carolina School of Medicine and lead investigator of the AFFIRM trial, previously told Healio. “One of the things we have learned with this class of medicines — the [interleukin]-23 p19 agents — is they seem to be incredibly safe for advanced therapies and highly effective.” As Healio has reported, the AFFIRM trial investigated efficacy and safety of subcutaneous risankizumab induction in 289 adults with moderate to severe CD. All study participants had a confirmed diagnosis for at least 3 months prior to enrollment and Crohn’s Disease Activity Index scores ranging from 220 to 450 at baseline. Researchers randomly assigned patients 2:1 to receive a 720 mg subcutaneous risankizumab dose at baseline followed by either 720 mg doses at weeks 2, 5 and 8 (n = 191) or placebo (n = 98). At week 12, risankizumab outperformed placebo in clinical remission (55% vs. 29.6%; delta = 26.6; 95% CI, 15.6-37.6) and endoscopic response (44% vs. 14.3%; delta = 29.4; 95% CI, 19.9-38.9). Similar results were reported among patients who had not received prior advanced therapy (clinical remission, 73.1% vs. 27.3%; endoscopic response, 61.2% vs. 15.2%) and those who were intolerant or had inadequate response to other biologic therapies (clinical remission, 45.2% vs. 30.8%; endoscopic response, 34.7% vs. 13.8%). According to the release, the most common adverse events related to risankizumab are upper respiratory infections, headache, joint and abdominal pain, injection-site reactions, anemia, fever, back pain, urinary tract infection and rash. “People living with Crohn’s disease need treatments that can deliver meaningful disease control from the start,” Roopal Thakkar, MD, AbbVie’s chief scientific officer and executive vice president of research and development, said in the release. “With the approval of subcutaneous induction, we are building on the strong efficacy of Skyrizi while giving patients and physicians greater flexibility in how treatment is initiated.” Published by: Ask a clinical question and tap into Healio AI’s knowledge base. PubMed, enrolling/recruiting trials, guidelines Clinical Guidance, Healio CME, FDA news Healio’s exclusive daily news coverage of clinical data Learn more Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Source link

How do you set yourself up for ergonomic success?
October 19, 2026 3 min read Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Click here to read the Healio Exclusive, “Practice good ergonomics early in career to avoid work-related injuries.” Now that I am in the middle of my career and approaching 51 years old, I feel like my body does not bounce back as well as it used to. I feel more tension in my back and sometimes in my shoulders. I used to be able to see patients all week, operate and feel great. I would not say I feel terrible at the end of the week, but I also know there has been a change over the last couple of years. As I have gotten more established in my career, I have gotten busier. I am doing longer surgery days and more cases, and that certainly plays a role. When I first started out, especially as someone in an academic setting, I was not super busy, and I had more time between cases. Now, I am jumping between rooms and always on the go on a surgical day. I have come to understand that ergonomics cannot be something I think about only during surgery. It has to be something that I am aware of all week long when I am seeing patients at the slit lamp, doing YAG lasers or performing other tasks. That all requires being mindful of ergonomics. Physicians are often making patients comfortable while making ourselves uncomfortable, but it is important to have a happy medium. I often ask patients to meet me in the middle and say, “Let’s make sure you’re as comfortable as you can be and I’m as comfortable as I can be so I can help you.” If they have trouble accommodating you, you can have family or a staff member help them sit up at the slit lamp so you are not overextending your neck and back. I try to be consistent with setup during surgery, including bed height, distance from me to the patient and distance from the oculars, but it can be a challenge. Not every patient can accommodate that. Recently, I had a patient whose cervical spine was completely fused, and in order to get him partially flat, we had to put him into the Trendelenburg position so his feet were up and his head was low. I was sitting low, and it was an awkward surgery to get through. Being more cognizant of my ergonomic habits in routine cases helped me to get through that case. One of the things that has made the biggest difference is finding out where the pain is coming from. A good friend is a physical therapist, and I had the chance to ask him why I was having so much lower back soreness and tightness. He told me it was my hips and gave me tips for stretches I could do. This helped me open up my hips and alleviate some of the tension. I should be doing this every day, and I try to do it at least a few times a week. There are some days that I come home and I will stretch while I am sitting and talking to my wife or watching a ball game. I will get on the floor in front of the TV and just do some stretches. Making that change has made a big difference in my lower back discomfort. I have also been trying to be more mindful as I get a little older by transitioning my exercise routine from more cardio to more strength training. I wanted to see if that helped me be a little more resilient, not just for work but for all aspects of life. As we get a little bit older, incorporating strength training is a way to maintain good health and longevity. When I work with young doctors, I try to impart that they have to develop these habits because it is not easy to fix the damage that can come from repetitive movements. For more information: Sumit “Sam” Garg, MD, a Healio | OSN Cataract Surgery Board Member, can be reached at gargs@hs.uci.edu. Published by: Sources/Disclosures Source: Healio Interviews Disclosures: Garg reports no relevant financial disclosures. Ask a clinical question and tap into Healio AI’s knowledge base. PubMed, enrolling/recruiting trials, guidelines Clinical Guidance, Healio CME, FDA news Healio’s exclusive daily news coverage of clinical data Learn more Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Source link

Subcutaneous infliximab outperforms IV maintenance in ileal Crohn’s
October 23, 2026 2 min read Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Key takeaways: Rates of clinical remission and endoscopic response and remission were higher with subcutaneous vs. IV infliximab in ileal-dominant CD. Additional prospective studies could confirm results. NASHVILLE, Tenn. — Patients with ileal Crohn’s disease had significantly better clinical and endoscopic outcomes at week 54 with subcutaneous vs. IV infliximab therapy, according to a presenter at ACG Annual Scientific Meeting. “Across every single endpoint, [subcutaneous maintenance] was better than IV maintenance for patients,” Marla C. Dubinsky, MD, codirector of the Susan and Leonard Feinstein Inflammatory Bowel Disease Clinical Center at Icahn School of Medicine, told attendees. Dubinsky emphasized the difficulties clinicians face when treating the ileal CD phenotype. Although surgical rates have decreased among patients with other types of inflammatory bowel disease — like ulcerative colitis — surgical rates for patients with ileal CD have yet to “catch up,” she said. “This is a very difficult-to-treat population, particularly [patients with] isolated ileal disease, just because of the [disease’s] fibrotic nature,” Dubinsky said. “We are typically operating.” Dubinsky and colleagues compared the efficacy of subcutaneous infliximab (Zymfentra, Celltrion) and IV infliximab (Remicade; Janssen, Johnson & Johnson) to determine whether patients with ileal CD “may preferentially respond better to one type of infliximab delivery over the other.” They collected data from four registrational trials for both subcutaneous and IV infliximab. A total of 200 patients across the trials met inclusion criteria, which included ileal or ileocolonic disease and treatment with IV infliximab 5 mg/kg every 8 weeks (n = 104) or subcutaneous infliximab at 120 mg every 2 weeks (n = 96). The pooled dataset was generally balanced by demographics and disease characteristics, although more patients treated with IV infliximab received immunomodulators at baseline (54.8% vs. 33.3%). The dataset remained well balanced after 1:1 propensity-score matching (total, n = 140). Dubinsky and colleagues assessed clinical remission and endoscopic response and remission in both unmatched and matched populations. Week 54 data showed patients in the unmatched population who received subcutaneous infliximab achieved significantly higher rates of clinical remission (76% vs. 55.8%, P = .003), endoscopic response (66.7% vs. 32.7%, P < .001) and endoscopic remission (41.7% vs. 18.3%, P < .001) than those who received IV infliximab. Outcomes were similar in the matched population, with subcutaneous infliximab achieving higher rates of clinical remission (71.4% vs. 51.4%, P = .023), endoscopic response (65.7% vs. 27.1%, P < .001) and endoscopic remission (41.4% vs. 17.1%, P = .003). Subgroup analysis of patients with ileal disease in the matched population showed subcutaneous infliximab outperformed IV infliximab in endoscopic response (52.2% vs. 18.2%, P = .029) and endoscopic remission (47.8% vs. 18.2%, P = .057). Rates of clinical remission also were higher with subcutaneous delivery, but did not meet statistical significance. Serum concentrations of infliximab were significantly higher among endoscopic responders than nonresponders with both subcutaneous and IV delivery. “This requires a lot more exploration and bigger [study populations],” Dubinsky said. “It was nice to see that we may have something that may have improved efficacy in isolated ileal disease when it comes to endoscopy, which is our most objective endpoint.” Additional prospective studies are needed to validate these results, the researchers noted. “As we think about how to position therapies, we need to think about phenotypes that may drive which treatment you should choose first or second based on [patients’] disease characteristics,” Dubinsky told attendees. Published by: Sources/Disclosures Source: Colombel J, et al. Comparative efficacy of subcutaneous vs intravenous infliximab in Crohn’s disease with ileal involvement: A pooled analysis and propensity score-matched analysis of infliximab registrational studies. Presented at: ACG Annual Scientific Meeting; Oct. 12-14, 2026; Nashville, Tenn. (hybrid meeting). Disclosures: Dubinsky reports advisory or consulting roles with AbbVie, Abivax, Amgen, AstraZeneca, Boehringer Ingelheim, Bristol Myers Squibb, Celltrion, Eli Lilly & Co, Genentech, Janssen, Johnson & Johnson, Merck, Novartis, Pfizer, Prometheus Labs, Sanofi, Spyre Therapeutics, Takeda Pharmaceuticals and Tentarix Biotherapeutics. Please see the study for all other authors’ relevant financial disclosures. Ask a clinical question and tap into Healio AI’s knowledge base. PubMed, enrolling/recruiting trials, guidelines Clinical Guidance, Healio CME, FDA news Healio’s exclusive daily news coverage of clinical data Learn more Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Source link
ASH guidelines aim to improve iron deficiency diagnosis
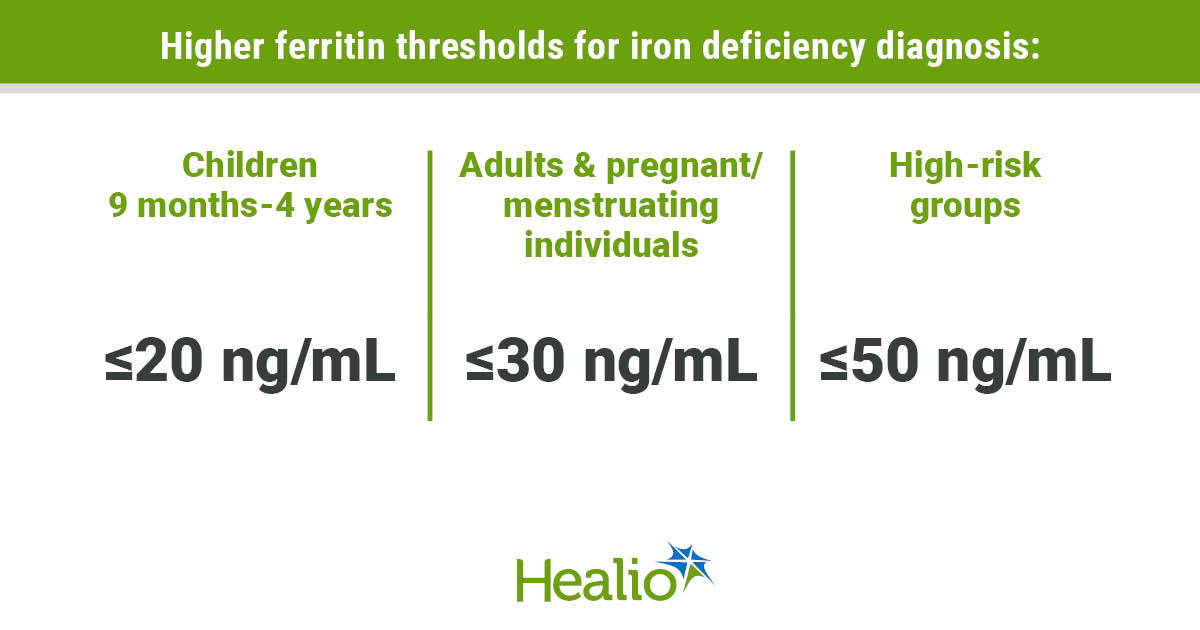
October 23, 2026 4 min read Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Key takeaways: ASH released new guidelines to improve iron deficiency diagnosis. Higher serum ferritin thresholds for multiple at-risk groups are intended to overcome variations in testing and diagnostic criteria. ASH has released new clinical practice guidelines designed to improve diagnosis of iron deficiency, the most common nutritional deficiency in the world. The guidelines recommend higher thresholds of serum ferritin — a protein that stores iron in cells — to improve diagnosis in multiple at-risk populations. Data derived from Powers J, et al. Blood Adv. 2026;doi:10.1182/bloodadvances.2025015950. The goal is to overcome variations in testing practices and diagnostic criteria to increase the likelihood that iron deficiency is identified earlier and more accurately, regardless of whether anemia is present. Angela C. Weyand “This condition affects billions of people worldwide. We know it can cause debilitating symptoms, and there are inexpensive, readily available medications to treat it, yet we’re not really doing anything about it,” guideline co-author Angela C. Weyand, MD, pediatric hematologist and clinical professor of pediatrics at University of Michigan Medical School, told Healio. “It is underdiagnosed, undertreated and understudied. In that sense, these guidelines are a huge step forward.” A problem before anemia Iron plays an essential role in hemoglobin production. It also regulates the immune system and supports brain function, according to background information provided in the guideline. About 14% of U.S. adults have absolute iron deficiency, meaning the body has run out of stored iron, according to a study by Tawfik and colleagues. Another 15% have functional iron deficiency, meaning sufficient iron is stored but it is trapped by inflammation, reducing the body’s ability to use it, the researchers continued. Guideline study background also specified that children and individuals who are pregnant or menstruating are at elevated risk, as are people with dietary restrictions, blood loss, or chronic conditions such as heart failure, kidney disease, inflammatory bowel disease or cancer. However, the majority of cases in high-risk populations go undiagnosed, Weyand said. If untreated, it can progress to iron deficiency anemia, which impairs oxygen transport in the body and can lead to life-threatening complications. “In medical school, most physicians learned about iron deficiency in the context of anemia,” Weyand said. “But iron plays so many other important roles in the body, and people don’t become anemic until they are severely iron deficient. There hasn’t been enough focus on the problems this can cause long before patients become anemic.” Several factors may contribute to underdiagnosis, Weyand said. Symptoms of iron deficiency — which include extreme fatigue, rapid heartbeat, shortness of breath, pale skin or headaches — can overlap with other conditions or may be attributed to psychosocial causes. Lack of consensus recommendations also has a role, Weyand said, noting neither the U.S. Preventive Services Task Force nor American College of Obstetricians and Gynecologists recommend iron screening during pregnancy. Higher ferritin thresholds Even when screening is performed, the ferritin thresholds used to diagnose iron deficiency vary widely. CDC and WHO use 15 ng/mL as the diagnostic threshold, but some physiologic studies of iron status and metabolism demonstrated thresholds of 25 ng/mL to 30 ng/mL — and possibly as high as 50 ng/mL — offer greater sensitivity. The ASH guidelines aim to provide some clarity by issuing conditional recommendations that suggest higher diagnostic serum ferritin thresholds for high-risk groups, including: 20 ng/mL or lower for children ages 9 months to 4 years, instead of 12 ng/mL or lower; 30 ng/mL or lower for adults and pregnant/menstruating individuals, instead of 15 ng/mL or lower; 50 ng/mL or lower for high-risk groups, such as those with heavy menstrual bleeding or pregnant individuals with anemia. Adults with inflammation — including those with infectious disease, cancer or inflammatory bowel disease — also are at risk. However, because inflammation is on a continuum, establishing a serum ferritin threshold for iron deficiency diagnosis has proved challenging. The guidelines recommend using a serum ferritin threshold of 100 ng/mL or lower, or a transferrin saturation below 20% for this group. Guideline authors emphasized the need for more evidence to strengthen the current conditional recommendations. Ideally, they would have found evidence to support thresholds of 50 ng/mL for all at-risk groups, Weyand said. “Because this topic has been underfunded and understudied for so long, we did not have the quality of evidence or caliber of studies needed to support that,” she said. “Another challenge is that we are relying on ferritin. It is the best option we have but, like most of our markers, it is imperfect. We are measuring what we can in the blood, but iron is important in so many different tissues and organs in our body. We don’t know anything about what iron is getting to our brain or to our muscles.” ‘No downside to checking’ An important next step will be spreading awareness in the clinical community about the ASH guidelines, as well as American Academy of Pediatrics guidelines issued earlier this year that recommend universal iron deficiency and iron deficiency anemia screening for all menstruating adolescent females who are at least 1 year post menarche, with screening to be done by age 14 years. “The biggest takeaway for the clinical community is how prevalent this is, and remembering iron is important to consider before anemia develops,” Weyand said. Clinicians should be mindful that widely used reference levels are “suboptimal,” Weyand said. This means some patients who previously underwent ferritin tests that did not identify them as iron deficient now may meet the more stringent criteria. She also emphasized ferritin is not a standard component of complete blood count (CBC),

Lily Allen Opens Up About Fear of Rejection and Her Own Pleasure
If you purchase an independently reviewed product or service through a link on our website, SheKnows may receive an affiliate commission. Lily Allen wasn’t always comfortable asking for what she wanted in bed. In a new interview with The Times, the singer said she focused on keeping her partner happy rather than considering her own needs. “My priority has been to make sure I don’t get rejected or abandoned,” she said. “Therefore, I’m prioritizing my partner’s enjoyment because the first thing I’m protecting is my safety.” Allen’s comments come as she launches a new collection with Lovehoney, which includes a cute peach-shaped clitoral stimulator, a heart-shaped dual clitoral and licking stimulator, and of course, her take on the famous Womanizer toy. Related story The Best Last-Minute Halloween Deals to Shop This Weekend — From Officially Licensed Costumes to Decor When it comes to sex, Allen said learning what she enjoys has helped her feel more comfortable asking for it — and she hopes talking about it will encourage other women to do the same. Lovehoney Lily Allen Heart Duo Clitoral Suction and Licking Stimulator Why Allen Put Her Partners’ Pleasure First “I grew up feeling that I was a vehicle for male pleasure,” Allen told The Times. “I never really considered my own needs.” For her, keeping a partner satisfied was tied to wanting to feel secure in the relationship, not necessarily enjoying herself. Allen also talked about how easily women can put their own desires last. “We don’t always prioritize our own desires because we focus on pleasing others, doing our jobs properly and looking after our friends and family,” she said in a press release shared with SheKnows. “We can forget that listening to what our body needs is just as important.” Speaking up wasn’t always easy for her, either. “I think women in particular can find it difficult to ask for what they want. When I was younger, I know I did,” she said. It’s something she wants to make less awkward to discuss, especially when the conversation is about self-pleasure. Lily Allen Womanizer Enhance Black Pleasure Air Clitoral Vibrator Learning What She Likes Has Helped Her Ask for It Allen said learning what she likes has made it easier to tell a partner what she wants. “For me, toys can help you to better understand your body and learn what you like,” she said in the Lovehoney press release. “I’ve been able to use that knowledge to express what I want in my relationships, which is empowering. And I hope this collection helps others feel similarly.” Allen told The Times that introducing toys with partners hadn’t always gone over well. But she’s no longer willing to give up something she enjoys to keep someone else comfortable. “I haven’t stuck around with [them] because I find [toys] really helpful, really fun,” she said. “It makes the whole thing a lot more enjoyable for me. If it makes it less enjoyable for him, he can move on.” Lily Allen Womanizer Peach Toy Rechargeable Clitoral Stimulator Allen first collaborated with Lovehoney in 2020. In the press release, she said people still tell her what a difference it made — and they’re not talking about her music. “Instinctively, I think they’re going to be talking about my music, but they’re actually talking about the toys,” she said. “Thankfully, people seem a little more comfortable now, but we still need to nudge that conversation along some more — it can only ever be a good thing not to feel shame about our own bodies.” For Allen, her own pleasure deserves time, too. “It’s not a selfish thing to do. It’s self-care — there’s no shame in it,” she said. “Why should we deny ourselves enjoyment and the confidence that can come from that?” Source link

Statement on Announcement of Executive Order on Women’s Health
HealthyWomen welcomes the Administration’s recent announcement of an Executive Order that would establish a new women’s health division within the National Institutes of Health, create a White House Women’s Health Task Force and coordinate a comprehensive approach to women’s health across all stages of life. Meaningfully advancing women’s health will take sustained commitment and collaboration across government, the healthcare community and the organizations that serve women. This order is an important step in mobilizing federal agencies around women’s health, and it builds on longstanding bipartisan efforts. As the White House Women’s Health Task Force convenes, we look forward to it translating the Order’s priorities into meaningful action, fostering collaboration, and identifying opportunities to strengthen research, innovation, education and access to care. For nearly 40 years, HealthyWomen has been a trusted voice in advancing women’s health, and we stand ready to work with the Administration to further our shared priority to improving women’s health across the lifespan. Source link


