

Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Key takeaways: At its annual meeting, the AMA adopted new policies stressing the need for physician oversight. They also advocate for more transparency when AI is used in both clinical and in health insurance decision-making. The AMA adopted new AI policies in a bid to ensure that the technology supports evidence-based medicine, bolsters patient care and serves under a physician’s oversight, instead of replacing their discernment. According to an AMA press release, AI technologies could help with efficiency and synthesizing information, but there are still important concerns for bias, long-term impact on both physicians and patient outcomes, explainability and transparency. At its annual House of Delegates meeting, the AMA adopted new AI-related policies. Image: Adobe Stock These new policies, which address AI’s growing popularity in both the clinical and health insurance decision-making realms, emphasize that AI should only be used as an assistive tool, rather than “an autonomous decision-maker,” according to the release. The policies also call for accountability, transparency and oversight from physicians every time AI is used in patient care. “AI has enormous potential in health care, but it cannot replace physician judgment,” John Whyte, MD, MPH, CEO of the AMA, said in the release. “Patients deserve care decisions that are informed by the latest medical evidence and guided by a physician who understands their individual needs. Whether AI is helping a physician make a clinical decision or assisting with an insurance review, there must always be transparency, accountability and meaningful physician oversight. Technology should support better care — not stand between patients and the care they need.” The AMA has said it will work with key stakeholders — including regulators, medical specialty societies and AI developers — to create standards for evidence transparency, evaluation, attribution, validation and explainability in systems that support clinical decision-making. This is in the hope of ensuring AI tools “reflect the principles of evidence-based medicine and provide physicians with information they can understand, evaluate and trust,” according to the release. Another AMA policy calls for regulations to guarantee that health coverage decisions — which are increasingly based on AI, according to the release — are reviewed by physicians in appropriate fields with a foundation of evidence-based, up-to-date medical information. The policy additionally called for safeguards requiring AI technologies be integrated into a physician-led process and increased transparency when AI is involved in prior authorization decisions, including the disclosure of any guidelines, data sources or clinical logic used in adverse decisions. In this vein, the AMA is advocating for regular audits of clinical review tools driven by AI to help strengthen accountability. That also includes audits triggered by “significant changes to” training data, clinical guidelines or AI models themselves, “as well as comprehensive annual reviews to ensure continued alignment with standards of care,” according to the release. “When health plans use AI-driven tools to deny or delay care without explaining how those decisions were reached, physicians and patients are left in the dark,” Whyte said in the release. “AI should never function as an unaccountable black box. Health plans must be transparent about how these tools work, what evidence and data sources they rely on, and whether a qualified physician reviewed the decision.” Perspective Back to Top The idea that AI should “support, not replace” physician judgment is not controversial. It’s obvious. The real issue is that, across health systems today, we are already drifting in the opposite direction — quietly, incrementally and often without enough oversight. AI tools are being embedded into workflows, influencing decisions and shaping clinical behavior faster than governance models can keep up. How many physicians are actually aware that they are using AI? The greatest risk is not that AI will replace physicians overnight. It’s that it will subtly erode clinical judgment through automation bias, opaque recommendations and overreliance on systems that clinicians neither fully understand nor control. In that sense, the danger is not disruption, it’s complacency. What the AMA policy stops short of saying explicitly is this: physician oversight alone is not enough. Oversight without infrastructure, governance and accountability is performative. Health systems need enterprise-level AI operating models — clear standards for validation, monitoring and lifecycle management — because fragmented, point-solution AI adoption is already creating measurable clinical and operational risk. Deepti Pandita, MD, FACP, FAMIA University of California Irvine Health Disclosures: Pandita reports no relevant financial disclosures. Sources/Disclosures Source: Press Release Disclosures: Whyte reports being CEO of the AMA. Ask a clinical question and tap into Healio AI’s knowledge base. PubMed, enrolling/recruiting trials, guidelines Clinical Guidance, Healio CME, FDA news Healio’s exclusive daily news coverage of clinical data Learn more Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio Source link

How Long Does an Epidural Steroid Injection Last?
If your doctor has recommended an epidural steroid injection to treat your back pain or another chronic pain condition, you probably have questions — especially about how long the relief will actually last. The honest answer is that it depends on the person, but understanding what affects duration can help you set realistic expectations and get the most out of your treatment. What Is an Epidural Steroid Injection? An epidural steroid injection (ESI) is a minimally invasive procedure used to relieve pain caused by inflamed spinal nerves. A physician injects a corticosteroid — sometimes combined with a local anesthetic — directly into the epidural space of the spine, which is the area surrounding the spinal cord and nerve roots. These injections are commonly used to treat conditions like herniated discs, spinal stenosis, degenerative disc disease, and sciatica. They’re one of the most widely used pain injections for back problems because they can reduce inflammation at the source, rather than just masking discomfort systemically the way oral medications do. How Long Does an Epidural Steroid Injection Last? This is the question most patients ask first, and the answer varies more than people expect. For some patients, relief lasts a few weeks. For others, a single injection can provide significant improvement for three to six months — or even longer. A smaller group of patients experience only minimal or temporary relief. Several factors influence how long the effects last: The underlying condition. Acute flare-ups of a chronic condition tend to respond better than long-standing, severe degeneration. How inflamed the nerve root is. The more targeted the inflammation, the more precisely the steroid can work. Your overall health. Factors like weight, activity level, and whether you smoke can all affect outcomes. The type and location of the injection. There are different approaches — interlaminar, transforaminal, and caudal — and the right technique depends on your specific anatomy and diagnosis. It’s also worth noting that the local anesthetic included in many injections provides immediate but short-lived relief — typically a few hours — while the steroid takes a few days to reach its full anti-inflammatory effect. So don’t be discouraged if you don’t feel dramatically better the same day. How Many Injections Will I Need? Most physicians recommend a series of up to three epidural steroid injections per year at any given spinal level. This isn’t arbitrary — repeated steroid use can have side effects, including thinning of nearby tissue or temporary changes in blood sugar levels. Some patients need only one injection per treatment cycle. Others benefit from two or three spaced a few weeks apart, especially when the first injection provides partial relief. Your pain specialist will assess your response after the first injection before recommending additional ones. The goal isn’t to keep injecting indefinitely. Epidural steroid injections work best as part of a broader pain management plan that may include physical therapy, lifestyle changes, and other treatments. What to Expect After the Injection Most patients go home the same day and can resume light activity within 24 hours. Some soreness at the injection site is normal and usually resolves within a day or two. Keep a symptom journal after your injection. Note when you start to feel relief, how significant it is, and how long it lasts. This information is incredibly useful for your care team when deciding whether to repeat the injection or explore other options. You should avoid strenuous activity, driving (on injection day), and submerging in water like pools or hot tubs for at least 24 hours after the procedure. Your provider will give you specific post-procedure instructions based on your situation. Are Epidural Steroid Injections Right for You? Epidural steroid injections are most effective for pain that has a clear inflammatory component — particularly radiating leg or arm pain caused by nerve compression. They tend to be less effective for purely mechanical back pain without nerve involvement. They’re not a permanent cure, and they won’t reverse structural damage like a severely collapsed disc. But for many patients dealing with injections for chronic pain management, ESIs offer a meaningful window of relief that allows them to engage more fully in physical therapy, return to work, or simply get back to daily life. Your pain specialist will review your imaging, medical history, and symptoms to determine whether this approach makes sense — and if so, which injection technique is most appropriate for you. Frequently Asked Questions How quickly does an epidural steroid injection start working? The local anesthetic may provide same-day relief, but the steroid component typically takes 3–5 days to reduce inflammation. Most patients notice meaningful improvement within one week. Can I get an epidural steroid injection if I have diabetes? Yes, but with caution. Corticosteroids can temporarily elevate blood sugar, so your care team will need to monitor you closely. Always disclose your full medical history before the procedure. Is the injection painful? Most patients report mild pressure rather than significant pain. A local anesthetic is used to numb the skin and underlying tissue before the injection, and many providers offer light sedation for anxious patients. How often can I get epidural steroid injections? Generally, physicians limit injections to three per year at a single spinal level to minimize steroid-related side effects. The timing between injections typically depends on your response to the previous one. What if the injection doesn’t work? If you receive little to no benefit from an ESI, that’s valuable diagnostic information. Your pain specialist may recommend a different injection approach, additional imaging, or an alternative treatment pathway. Taking the Next Step Toward Relief Living with back pain or chronic pain is exhausting, and it’s easy to feel like you’ve run out of options. Epidural steroid injections aren’t a cure-all, but for the right patient, they can be a genuine turning point — one that creates enough relief to move forward with therapy, regain function, and improve quality of life. If you’re weighing your options, the best next step is a conversation with

My Chronic Hives Kept Coming Back
Español As told to Erica Rimlinger The hives first appeared when I was in my early 20s, following a trip to the laundromat. Putting on my newly clean clothes, a rash perfectly outlining the shape of my bra and underwear formed. Shocked and incredibly itchy, I called my mom, who guessed I used too much detergent in my laundry or was having an allergic reaction. She recommended an antihistamine, which didn’t even take the edge off the never-ending itch. Unable to sit down or tolerate clothing touching my angry, red welts, I called the Ask-a-Nurse hotline my health insurance required. After an hour on hold, I was cleared to go to their urgent care. There, a doctor gave me a steroid shot and wrote me a prescription for several days of steroid pills. He told me to stay on an antihistamine and advised against using that detergent brand again. The angry, red hives quickly cooled to pink, calmer ones, then, nearly a week later, disappeared. I thought this episode was a learning experience and that it was over. But it wasn’t over: The hives returned. Each time, my healthcare providers and I assumed some unknown allergen had irritated me. I’d get a course of steroids, keep taking antihistamines and the hives would disappear like magic over the next week. I didn’t care about any long-term side effects of taking steroids: I just needed them to work when I needed them. I kept detailed notes on what I ate and used on or near my skin. I saw an allergist, who couldn’t find a culprit that was causing the outbreaks. In my 20s and 30s, the outbreaks were relatively short, but I’d have to miss life for a week while I dealt with them. The itch was too intense to allow me to focus on anything for very long, and no cream, pill or treatment provided enough relief. In my 40s, the hives were staying longer and not responding quickly to the steroids or multiple antihistamines. By then, when the outbreaks lasted well over a week and felt unmanageable, I was desperate for relief. If you’re imagining hives as a collection of small, red, itchy bumps like mosquito bites, you’re not quite getting the full sensory experience. My hives erupted in painful swells that couldn’t be touched without angering my body and making the itch even worse. It was as if someone shaved off all my skin with a razor and covered me with wool. During my flares, a light scratch of the fingernail along my skin would turn the line into hives. I could write my name in hives on my skin, a phenomenon called dermatographism. In 2019 I had a hive outbreak that lasted months, meaning my hives met the definition of “chronic.” As I had with shorter outbreaks, I found it nearly impossible to work, sit, function or do simple activities like bathing. I had hives every day and didn’t know which days they might be more severe or where the swelling and itching would move to next. The painful itch was oppressive — and nothing relieved it. During flares, I continued to document all the details of my life, looking for any reason for the outbreak’s appearance, disappearance, worsening or relief. I couldn’t find a pattern, an allergen or any clue why this was happening. During my last flare, I also couldn’t find any form of relief that worked anymore. There are many myths about chronic hives, and one is that simply reducing stress eliminates outbreaks. As a woman experiencing a chronic illness, I found medical staff commonly telling me if I would just be calmer, I wouldn’t be sick. But, my regular notetaking about the circumstances surrounding my outbreaks showed me they were not caused by my emotions. It felt dismissive for people to imply I could control the extreme physical reaction my body was having by simply not being stressed — as if that were even possible. CSU on Kristen’s legs The first week of the 2019 outbreak was the worst agony I’d ever experienced, then the outbreak lost predictability entirely. I could not sit still given how severe the itching was. It prevented me from sleeping, working, being with friends and family, and doing basic activities. After a few days, things improved, but the hives were still present every day: first for weeks, and then months. A while back, I’d been diagnosed with an autoimmune disorder called Graves’ disease. I wondered if my hives could be related. After some research and consulting with my immunologist, I learned about chronic urticaria (CU), or chronic hives. In most people with the condition, its cause is never identified, which is called chronic spontaneous urticaria (CSU) — but the outbreaks are strongly linked to autoimmune issues. I was taking steroids and quadruple doses of antihistamines, and they provided no long-term relief. I finally found an allergist/immunologist who knew that CSU is almost never an allergic reaction — despite common misconceptions. She knew what to do next and that gave me great hope. I continued taking antihistamines and started a treatment that required a shot in the back of each arm each month. By month three, I hadn’t seen improvement. I called a friend who is a pharmacist and asked, “Is this going to be forever? Why can’t I get rid of these?” The friend contacted a trusted colleague in the field who told me to stick with it, so I did. Almost like clockwork, by month six, the hives were completely gone. I could cry just thinking about it today. What an incredible relief. Since that time, I have not had an outbreak. While I’ve had an occasional, isolated hive, I’ve had no flare-ups since. I didn’t intend to become an advocate for people with chronic hives, but I was working for a global patient advocacy organization that included CU in its scope of work. When I mentioned to my CEO that I was a CU patient

Natalie Morales on Alzheimer’s and Caregiving
CBS correspondent Natalie Morales is 54, the same age her mother-in-law was when she received a devastating Alzheimer’s diagnosis. So when Morales experienced a memory lapse while on a recent work trip, she couldn’t help but fear the worst. “I’m very well aware of when I have a memory lapse, whenever there’s a word I can’t think of,” Morales told USA Today in an interview this week. “Or if, you know, I know this person but… I can’t think of their name.” On her trip, Morales forgot her hotel room number, spending minutes on the wrong floor tapping her key card against doors. “Oh my gosh,” she remembered thinking. “Either I’m overworking, or I don’t know what’s going on. Maybe I’m having perimenopause brain.” Of course, the thought of dementia also ran through her mind. Her mother-in-law, Kay Rhodes, died in 2014 after living with Alzheimer’s for years. Related story Olivia Munn Describes ‘Surreal’ Breast Cancer Diagnosis: ‘I’d Seen This in Movies’ Morales doesn’t have dementia, but fearing it is understandable — once we get to a certain age, it’s hard not to. That’s especially true when it’s impacted your loved ones. “I think she was always a little bit afraid of getting that diagnosis,” Morales said of her mother-in-law. “And there was a little bit of that denial, although I think she knew better than anyone what she was feeling.” The first signs, Morales remembers, were her mother-in-law having trouble completing tasks and repeating herself while speaking, along with anxiety and paranoia. Rhodes’s struggle with Alzheimer’s also impacted the rest of the family. Rhodes’s husband was her primary caregiver and Morales says he felt the impact physically, emotionally, and financially. “With a lot of caregivers, you know, the more they invest in someone else and in that care, they lose themselves in that,” Morales reflects. Now that Morales herself has some of those same Alzheimer’s fears, she’s both accepting and optimistic about the future. “We are at that age where these are things that we have to talk about and think about a lot more,” she said. But thanks to medical advancements, there are now more treatments than ever for people with dementia, including new medicines, better testing, and drugs that stop Alzheimer’s triggers. “The outlook,” Morales agrees, “is so much more positive now.” Source link
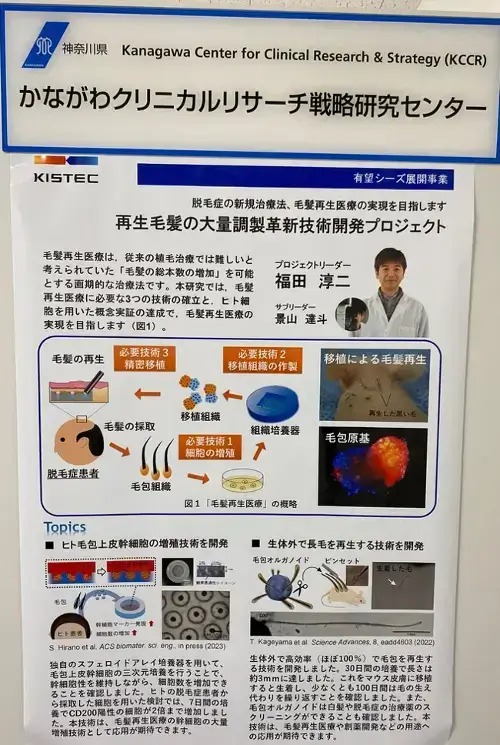
A Visit to Fukuda Lab at Yokohama National
This post was originally written in 2024. I have added new updates from 2025 and 2026 at the bottom. I have extensively covered the work of the esteemed Japanese hair loss researcher Dr. Junji Fukuda for over ten years. Among the posts that I have written in relation to his team’s work at Fukuda Lab include the following: February 21, 2024 A Visit to Fukuda Lab at Yokohama National Reader “Theo” just sent me a link to a very interesting diary of a hair transplant surgeon from Japan who just visited the Fukuda Lab. Note that while Dr. Fukuda is based at Yokohama National University, the research seems to be taking place at Kanagawa Life Innovation Center (per the above link). One of the images also mentions the Kanagawa Center for Clinical Research & Strategy (KCCR). Yokohama is the second largest city in Japan and is the capital of Kanagawa Prefecture. Check out this PDF of the regenerative medicine sector at Kanagawa Prefecture. From this visit and summary, I learn some very interesting things. There are three distinct methods in which Dr. Fukuda is pursuing hair regeneration. I mentioned them in my past lengthy post too, but now we have more clarity. 1) Dermal Papilla Cell Transplantation “Dermal papilla cell transplantation is about to begin in Japan.“ Transplantation of dermal papilla cells (via stratified culture). I assume that the “stratified cuture” in the translation means 3D culturing. Dr. Fukuda mentions that Shiseido already conducted a clinical trial using 2D culturing. In this method, cells are are lined up on a flat surface when culturing, but it only resulted in a 5% increase in hair volume. The 3D method will likely be superior and the clinical trials are about to finally begin! It is hoped to be “put into practical use within five years”. 2) Transplantation of Hair Follicle Primordium “I think this will take some time.” The creation of hair follicle primordia means generating hair from scratch. i.e., hair multiplication. I previously discussed the Yokohama team’s process of achieving this via increasing and mixing epithelial cells and mesenchymal cells. These then form “hair follicle primordia“ that are transplanted to the same donor’s scalp in order to regenerate hair in thinning regions of the scalp. Per the latest feedback from Dr. Fukuda, while this process has already been proven by them in mice, human hair is a different animal. Once the primordium tissue is transplanted to human heads, the direction and length grow haphazardly. He thinks that this will take some time. 3) Transplantation of Regenerated Hair Follicles in Vitro (Organoids) “It will likely take more than 10 years before it can be used in humans.” The final method is in vitro regenerated hair follicle transplantation (also called organoid). In this process, hair follicles are regenerated outside the body, lengthened by almost 100%, and then transplanted into the scalp. Per Dr. Fukuda, it will likely take more than 10 years before it can be used in humans. Other Notes In March 2023, Dr. Fukuda and his Yokohama team published an important hair regeneration related study. They made an improvement in the expansion of hair follicle stem cells (HFSCs) and dermal papilla cells via the use of a newly designed microwell array device. Fukuda Lab’s hair research summary poster. Source:Naohiro Uchida, Director of Almo Plastic Clinic Hair Transplantation. Update: April 18, 2024 New Junji Fukuda interview given to Tokyo Television. Someone please translate it into English if you know Japanese. Not yet on YouTube. Junji Fukuda TV Interview. Update: June 15, 2025 Yet Another Visit to Fukuda Lab Yet again, Tokyo TV visited world renowned hair loss researcher Dr. Junji Fukuda at Yokahama National University. A Japanese reader posted a link to the full video in the comments, but it did not load for me. However, I managed to find two of the segments on YouTube. You can turn on English captions in the videos. The Japanese viewer comments underneath the first video are funny. Update: June 12, 2026 A number of new updates in recent months. In December 2025, Dr. Fukuda gave an interesting interview. He said that his team’s initial goal is to popularize hair regeneration therapy, thereby establishing the necessary infrastructure (such as cell processing facilities). In the future, they aim to expand this technology to regenerative medicine for various organs, in particular, the liver. Quote: “Hair is naturally formed by two types of cells (epithelial cells and mesenchymal cells) exchanging information with each other. We are challenging ourselves to unravel the mechanism of this “interaction” and completely reproduce it in a culture dish. In fact, most of the organs in our bodies are formed by the interaction of these two types of cells.” Of note, Dr. Fukuda is described as the President and CEO of TrichoSeeds, a company he co-founded several years ago. He also continues to work at Yokohama National University via Fukuda Lab as a professor and researcher. In March 2026, Dr. Fukuda co-authored a paper on the potential of employing hiPSC-derived ectodermal precursor cells in hair follicle organoid cultures in hair regenerative medicine. In April 2026, it seems like the Fukuda Lab got some funding from Beyondge Capital (Japan). Also in April 2026, Dr. Fukuda gave a presentation titled: “Treatment of male pattern baldness using microRNA produced by human papilla cells in stratified culture.” In April, Dr. Fukuda and his team authored yet another paper. They discuss their findings about the correlation between reduced CD200 expression and increased hair regenerative capability of cultured hair follicle bulge cells. Quote: “Our study refines the functional interpretation of CD200-defined bulge heterogeneity and provides insights for optimizing human bulge cell-based approaches to hair follicle regeneration.“ Source link

New tool launched to help improve headache and migraine care
This week, The Migraine Trust and The Neurological Alliance launched Improving headache and migraine care together: A tool for NHS professionals & providers. The new tool is designed to help NHS commissioners, providers and professionals to plan, design and improve local services for people of all ages affected by headache and migraine. It identifies and signposts to the best available resources and provides a framework for local service transformation. Developed by The Migraine Trust and the Neurological Alliance with support from people living with migraine, health professionals, service managers at Integrated Care Boards (ICBs) and NHS provider representatives from across England, the tool is focused on care pathways that can be delivered in the community with key stakeholders, partners and services. Rob Music, Chief Executive of The Migraine Trust, said: “We know that many people with migraine find it challenging to access the care they need or deserve. At the same time, we recognise it can be challenging as a commissioner, provider or healthcare professional looking to improve services to know where to start. The launch of this tool marks an important step in moving toward consistent, high-quality care for people living with migraine.” Georgina Carr, Chief Executive of Neurological Alliance, said: “This tool offers a blueprint for best practice headache and migraine care in local settings and supports the NHS 10 Year Plan’s ambition to move care from hospitals to communities. We hope it will empower local healthcare leaders to improve headache and migraine services, which will not only improve patient outcomes but also reduce pressure on secondary care services.” Improving headache and migraine care together: A tool for NHS professionals & providers is endorsed by the British Association for the Study of Headache (BASH), Association of British Neurologists (ABN) and British Paediatric Neurology Association (BPNA). Alex Sinclair, Chair of BASH, said: “BASH welcomes this practical, evidence-informed tool, which brings together the key resources needed to improve headache and migraine care across the NHS. By supporting joined-up pathways, strengthening primary and community management, and enabling timely access to specialist expertise, it represents an important step towards more consistent, high-quality care for people affected by headache disorders.” Dr Rachael Kilner, Clinical Advisor on the project, GP with extended role headache King’s College Hospital, St Thomas’ Hospital and Bromley GP Alliance community headache clinic, said: “Headache disorders represent one of the largest opportunities to improve neurological care across the NHS. Too many people are still experiencing avoidable delays, unnecessary referrals and fragmented pathways. This tool brings together the evidence, clinical guidance and practical resources needed to support more consistent, joined-up care across primary, community and specialist services.” Dr Kay Kennis, Clinical Advisor on the project, GP with extended role in headache, Bradford Community Neurology Service, said: “For many people living with migraine, the difference between good and poor care comes down to whether they can access the right support at the right time. Strengthening headache care in the community has the potential to improve outcomes for patients while reducing avoidable demand on hospitals. This tool supports services to make those changes using evidence-based approaches.” The Migraine Trust is committed to improving care, support and awareness for people with migraine. You can stay up to date with our work here and by signing up to our ebulletin. Financial support for this project has been provided as a Quality Improvement Grant from Pfizer International LLC. Editorial control rests with The Migraine Trust and the Neurological Alliance. Source link

Ambient AI in the exam room: Friend or foe for physicians?
June 12, 2026 11 min read Add topic to email alerts Receive an email when new articles are posted on Please provide your email address to receive an email when new articles are posted on . “ data-action=”subscribe”> Subscribe We were unable to process your request. Please try again later. If you continue to have this issue please contact customerservice@slackinc.com. Back to Healio As the presence of ambient AI scribes to record clinical encounters in the exam room grows increasingly common, experts continue to debate over whether this new technology will ultimately be a friend or foe to physicians. “Ambient AI has the potential to bring about significant changes in what has become the elephant in the room for many physicians: the electronic health record,” Leonard H. Calabrese, DO, chief medical editor of Healio Rheumatology, professor of medicine at the Cleveland Clinic Lerner College of Medicine of Case Western Reserve University, and RJ Fasenmyer chair of clinical immunology at the Cleveland Clinic, said in an interview. Image: Allan Gibofsky, MD, JD, MACR, FACP, FCLM For example, ambient AI can listen to clinical encounters and minimize the time physicians spend on electronic health records, which experts have long cited as a source of bureaucracy-related burnout. However, whether those changes are immediate or universally positive remains to be seen, according to Kenneth G. Saag, MD, MSc, professor of medicine in the division of clinical immunology and rheumatology at the University of Alabama, Birmingham. Kenneth G. Saag “Ambient AI has the potential to alleviate a pretty major challenge, which is that most of the clinical encounter is spent typing,” he said. “But we have to consider whether the AI scribe is capturing salient details and weeding out the chatter.” According to Saag, an ambient AI tool could, in a perfect world, do exactly that and potentially bring back the kinds of doctor-patient encounters he recalls from a generation ago. “It can allow us to look the patient in the eye and return to the interpersonal nature of a doctor visit,” he said. “The hope is that it is not creating more work by requiring a lot of editing.” For Allan Gibofsky, MD, JD, MACR, FACP, FCLM, professor of medicine at Weill Cornell Medicine, and attending rheumatologist and co-director of the Clinic for Inflammatory Arthritis and Biologic Therapy at the Hospital for Special Surgery, the risk for introducing errors into the medical record should be top of mind for any physician. “As with any new technology, we have to temper our enthusiasm for its utilization with caution of how it is going to be utilized,” he said. “For example, what does it mean to use this tool without appropriate professional oversight? Medical records are eternal. If there is an error in a patient’s chart, it gets carried forward and attempts to correct it are, at best, problematic. It is important that the same is not true for the documentation by AI scribes.” Another potential concern is that employers may see the time-saving nature of these products and adjust employee expectations accordingly, said Grace C. Wright, MD, PhD, of Grace C. Wright MD PC. Grace C. Wright “Time is money, and if AI allows you to see patients more efficiently in less time, the patient load may be increased,” she told Healio. “I would prefer to have more issues dealt with in the clinical encounters, such as mental health, life impact and social connectedness, instead of just adding more patients. Undoubtedly, our patients would become healthier if we could spend the extra time managing their overall health.” Additional concerns over the use of ambient AI in the exam room involve potential threats to patient privacy, and the question of when and how to acquire patient consent to use such technologies. However, if these impediments can ever be overcome, the technology could fundamentally alter the way medicine is practiced, according to experts. ‘Redesign the choreography’ In a 2025 paper published in JAMA Network Open, Olson and colleagues surveyed 451 physicians who used an AI scribe in the clinic for 30 days to determine whether use of the technology saved them time and reduced burnout. Among the 272 physicians from multiple specialties who completed both the pre- and post-intervention surveys, results at 30 days showed that the proportion of respondents who reported experiencing burnout decreased significantly from 51.9% to 38.8% (OR = 0.26; 95% CI, 0.13-0.54). Further results showed that use of an ambient AI scribe was associated with significant improvements on a 10-point scale in burnout (mean difference, 0.47 points; standard error, 0.12), note-related cognitive task load (mean difference, 2.64 points; standard error, 0.13), ability to provide undivided attention (mean difference, 2.05 points; standard error, 0.18), patient understandability of their care plans from reading the notes (mean difference, 0.44 points; standard error, 0.17), and time spent documenting after hours (mean difference, 0.90 hours; standard error, 0.19). “This multicenter quality improvement study found that use of an ambient AI scribe platform was associated with a significant reduction in burnout, cognitive task load, and time spent documenting, as well as the perception that it could improve patient access to care and increase attention on patient concerns in an ambulatory environment,” the researchers wrote. Although Calabrese said he is encouraged by such findings, he noted that simply having the tool is insufficient to reshape the clinical experience. Leonard H. Calabrese “This technology has the potential to redesign the choreography of the practitioner-patient dyad that has been with us for 20 years since we have been using the laptop and the EHR,” he said. “However, I have strong doubts that everyone who starts using ambient AI will be on a trajectory to optimize their practitioner-patient interaction spontaneously just because there is a device recording your voices.” According to Calabrese, there is a perception that younger physicians will be more adaptable to the new technology. However, he suggested that practitioners of all ages could experience some discomfort in the way
Bastrop – Dr. Parris Departure Letter
Bastrop – Dr. Parris Departure LetterDownload <p>The post Bastrop – Dr. Parris Departure Letter first appeared on Pain Specialists of America | For Every Pain, We Have a Plan..</p> Source link

5 Foods for Brain Health
June is Alzheimer’s and Brain Awareness Month. If we are what we eat, what happens when you’re equal measure sugar-free coffee creamer and chicken salad (asking for a friend)? Short answer: You may want to rethink your diet. And while you’re thinking, add in some ingredients that can help boost your brain health. Eating plans such as the MIND and DASH diets incorporate anti-inflammatory foods such as leafy greens, fatty fish, nuts and olive oil that have positive effects and may even help slow aging in the brain. One recent study of mostly women found participants who followed the DASH diet were associated with a lower risk of cognitive decline and better cognitive function (thinking, learning, remembering) compared to people who didn’t follow the diet. When it comes to brain-boosting ingredients, produce is usually queen. Studies show foods rich in flavonols — a group of plant-based compounds with anti-inflammatory and antioxidant properties — can help improve cognitive function and reduce the risk of neurodegenerative conditions like Alzheimer’s disease. Keeping your brain as healthy as possible is especially important for women because women are at higher risk for Alzheimer’s disease and worse cognitive aging compared to men. Here are 5 foods to incorporate into your eating plan to help keep your brain sharp. 1. Fatty fish iStock.com/tbralnina There are plenty of fish in the sea, but salmon, sardines, anchovies, mackerel and herring are among the best for brain health. These under-the-sea snacks are rich in omega-3 fatty acids, namely docosahexaenoic acid (DHA), that your brain needs to build and repair brain cells among other important functions. Consuming omega-3 fatty acids also can help protect memory and support cognitive thinking. One study of mostly women found participants who ate fatty fish at least twice a week had a lower risk of developing brain changes linked to dementia compared to the group who didn’t eat the fish. Feed your brain: 8 ounces per week — about the size of two decks of cards lying next to each other 2. Blueberries iStock.com/Maksym Narodenko Blueberries are the Super Woman of the fruit universe when it comes to protecting against neurological decline. Their super power comes from their blue pigment — a flavonoid called anthocyanin — which has antioxidant and anti-inflammatory properties. Research shows consuming blueberries can improve the speed of brain processing, protect memory and improve brain function among other benefits. And you can pair these little blue beauties with other berries for a brain boost. One study found women who consumed two or more servings of blueberries and strawberries a week delayed memory decline by up to 2.5 years. Feed your brain: 1/2 cup to 1 cup per a day 3. Avocados iStock.com/Volodymyr Rozumii Did you know that Audrey II — the plant from Little Shop of Horrors — is a cross between a Venus flytrap and an avocado? Well, it all makes sense considering avocados feed your brain with monounsaturated fats — the “good” fats — and antioxidants like lutein that can help improve blood flow and have a positive effect on memory. One study found people who consumed avocados showed significantly better immediate and delayed recall and overall cognition compared to the group who didn’t eat avocados. Pass the guacamole! Feed your brain: About half of an avocado a day 4. Walnuts iStock.com/Oleh Muslimov Sometimes you feel like a nut, and when it comes to brain health, that nut should be a walnut. Fun fact: Walnuts are the only nuts that have significant amounts of alpha-linolenic acid (ALA) — an omega-3 fatty acid essential for protecting brain health. Walnuts also have antioxidant and anti-inflammatory properties that fight oxidative stress and inflammation in the brain. Studies show adding a daily dose of walnuts can boost memory and delay age-related cognitive decline among other brain benefits. Bonus: The antioxidant effects of walnuts can reduce the risk of other health conditions like cardiovascular disease that are risk factors for Alzheimer’s. Feed your brain: About 1/4 to 1/2 cup (7 to 14 whole walnuts a day) 5. Dark chocolate iStock.com/SherSor We didn’t forget about all the sweet tooths out there. Or, rather, Mother Nature didn’t. Dark chocolate is packed with cocoa flavanols that improve cerebral blood flow and protect against damage to brain cells. One study of midlife adults found that the group who ate five pieces of 72% dark chocolate a day for a month showed improved executive functioning such as problem-solving and focus, memory and increased gray matter volume, which is associated with memory and an important indicator of good brain function. The sweet group also reported less fatigue than the group who did not eat dark chocolate. It’s important to note that all dark chocolate is not the same. You want dark chocolate with at least 70% cacao to get the brain-boosting benefits and the higher the percentage, the more flavanols and antioxidants it has. Feed your brain: About one to three squares of dark chocolate up to six times a week — bonus brain points for dark chocolate with walnuts. From Your Site Articles Related Articles Around the Web Source link

Nutrition for the Luteal Phase: Fighting Cravings and Bloat
Feeling crampy, bloated, and ravenous right before your period? During the luteal phase of the menstrual cycle, hormonal surges and dips can cause unpleasant symptoms such as spikes in appetite and water retention. If period cravings are driving you to devour every empty calorie in sight, here are some luteal phase diet tips to ensure your body gets the nutrition it needs to fuel your activities and minimize discomfort. Why Do I Get So Hungry During The Luteal Phase? The luteal phase of the menstrual cycle happens around day 15 to 28 of the cycle. This is the run-up phase after ovulation, beginning after an egg is released into the uterus and lasting until either the egg is fertilized (pregnancy) or shed through menstrual bleeding. Since your body is essentially preparing for a pregnancy, several hormonal shifts occur which can have you reaching for that second bag of chips or wanting to demolish a whole chocolate cake. Estrogen Goes Down Estrogen is a hormone that suppresses appetite and boosts mood. In the days leading up to your period, estrogen levels fall, which can lead to mood swings and increased hunger. Progesterone Dominates Progesterone stimulates appetite – perhaps so your body is properly fueled in case pregnancy occurs – and while progesterone levels go down right before menstruation, lower levels of estrogen means progesterone becomes the dominant hormone. Depleted Serotonin Serotonin, aka our “happy hormone,” also goes down around this time. The “comfort” in comfort foods comes from how consuming high-carb, sugary foods triggers a rush of serotonin, making them extra tempting – especially when annoying PMS symptoms like fatigue, bloating, cramps, and irritability are compounding the period blues. Scrambled Satiety Hormones Ghrelin and leptin are hormones that tell our body when it’s hungry or full. Fluctuations in progesterone and estrogen also interact with ghrelin and leptin, messing with our satiety cues and spiking appetite. Your Metabolism Rises, Slightly Resting metabolic rate (RMR) is the amount of energy your body uses at rest. Studies have found a small increase in RMR during the luteal phase, potentially due to a progesterone-driven increase in body temperature. This means that you may be burning slightly more calories than normal at certain times of the month. However, the increased calorie expenditure is minute – closer to an extra protein bar or avocado than the family-sized bag of chips you may be craving. Best Foods To Eat PMS cravings are a natural part of menstruation. There’s nothing wrong with curling up in bed with a box of chocolate once in a while, but it’s also important to give your body plenty of nutrients to balance PMS symptoms like bloating and fatigue. Here’s what a nutrient-rich luteal phase diet can do for your PMS symptoms: Stabilize your blood sugar, helping you keep mood and energy levels up Ease bloating by reducing water retention and inflammation Help your body produce and regulate progesterone production Boost serotonin levels Help you cramp less Magnesium-Rich Foods Magnesium is the MVP of PMS nutrients, helping reduce water retention, muscle cramps, and sleep issues. Studies have found that supplementing magnesium can actually reduce PMS symptoms like anxiety and irritability. Some good sources of magnesium include: Pumpkin seeds Dark chocolate (stick to chocolate with 70% cacao or more for your chocolate cravings!) Leafy greens like kale and spinach Nuts like cashews, almonds, and brazil nuts Bananas Avocados Legumes like black beans and edamame Support Your Hormones with Vitamin B6 Vitamin B6 supports progesterone production and acts as a coenzyme in the synthesis of neurotransmitters like serotonin. Eating plenty of Vitamin B6 can help regulate the period blues that come with decreased serotonin. Good sources of B6 include: Lean chicken and turkey Fish and seafood like salmon, halibut, and tuna Organ meats like liver are particularly high in vitamin B6 Starchy vegetables such as sweet potatoes, yams, and different types of squash Spinach Tropical fruits like pineapple and mango Nuts and seeds like pistachios, sunflower seeds, and chia seeds Pairing Calcium and Vitamin D To Reduce PMS Symptoms Low levels of vitamin D and calcium can exacerbate PMS symptoms. Research shows how a high combined intake of vitamin D and calcium can ease bloating, mood swings, and pain. Calcium-rich foods: Dairy products like greek yogurt, kefir, and cottage cheese Almonds Dark leafy greens Fortified plant milks Edamame and tofu Almond While vitamin D is difficult to get from food alone, going for a walk in the sun or taking a supplement can help. Foods containing vitamin D include red meat, oily fish like salmon and sardines, and egg yolks. Low-Inflammatory Recipes for Period Prep As anyone who has had to work, run errands, or take care of children knows, life doesn’t pause for your period. Having a game plan when tackling the luteal phase can help you pack in the necessary nutrients for a smoother period. Eating a combination of complex carbs, plenty of protein, and fiber to support digestion (period constipation is real!) will keep energy levels up and ease mood swings. Here are some meal ideas to combat inflammation and keep energy levels up when you most need it. Steel-Cut Oats with Yogurt, Chia Seeds, Greek Yogurt, and Honey The complex carbs in oats keep your blood sugar levels steady and boost serotonin production. Greek yogurt is full of protein, keeping you fuller longer and away from processed snacks! Fiber and probiotics will boost digestion – Progesterone can slow digestion during the luteal phase, which is why some people feel constipated right before their period. For an extra anti-inflammatory boost, add a spoonful of omega-3 rich chia seeds, which helps with cramps, and soothe that sweet tooth with honey (natural antioxidant). You can even add some dark chocolate to replenish serotonin. Tofu, Edamame, and Chopped Kale Salad Edamame beans are a great source of protein, calcium, and omega-3 fatty acids. For an easy, no-cook salad, buy frozen packets of edamame and shell into some hot water to thaw. If you have trouble


